The four elimination pathways and Coronavirus or:
Medicine is not a science but an opinion.

The obligation for masks is considered one of the most effective measures to combat the coronavirus pandemic. This measure is imposed, like many others, only for populist political reasons and is not only completely ineffective with regard to a reduction in the transmission of the virus, but also constitutes a serious danger to the health of anyone wearing the mask (1) (European Centre for Disease Prevention and Control 2020). This problem is sidetracked, deliberately creating great confusion among the sick, the dead, the HIV-positive, the healthy carriers, the asymptomatic, the positive etc.

In the end the contagiousness index was introduced (Robert Koch Institute) as the supreme judge of good and evil, which arbitrarily divides countries into zones of good and bad citizens, the latter to be ruthlessly punished. All this happens with no scientific basis and is statistically unacceptable, but the hunt for positives with all available means (immune App etc.) has become one of the “main weapons in the fight against the Coronavirus”. Those discovered positive and their families are put under house arrest and pilloried, as if they were criminals.

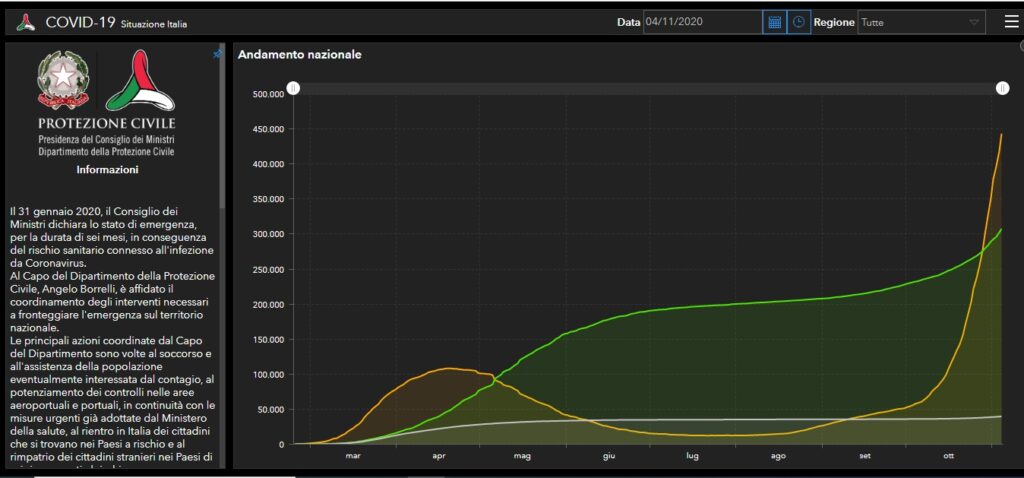
But this  hunt makes no sense, as the contagiousness index is completely unrelated to mortality, as shown by the statistics issued  by the Italian Ministry of Health/ Ministero della Salute Italiano on 4/11/20 (2).
casi covid
Curve – yellow: currently positive, green: recovered, grey: deaths

BUT WHAT IS WRONG WITH MASKS?

I’ll explain it in a nutshell.

Our body has four elimination pathways for noxious substances: urinary tract (urine), digestive tract (feces), skin (perspiration) and the lungs (respiration). This last pathway, important with regard to coronavirus transmission, must guarantee both the oxygen/carbon dioxide exchange and the ventilation of the respiratory tracts, the nasal and paranasal sinuses and the middle ear.

If this or any other pathway is interrupted or reduced, the body gets progressively intoxicated and damaged even irreversibly.

And now we come to masks:

  1. Masks in no way protect against coronavirus infection as the means of transmission is exclusively aerial by aerosols (3) and not through droplets or contact.

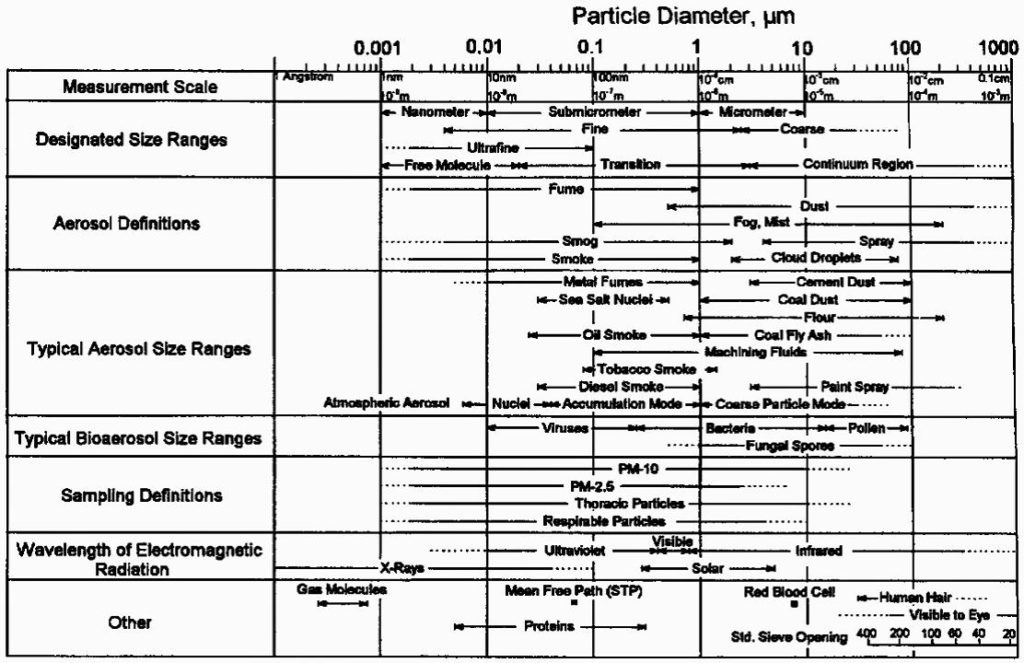
The Coronaviruses have a superimposable shape to that of various pollens (one of nature’s wonders) but they are much smaller and are transmitted in the same way, suspended and transported by air. If they land on fertile ground (for the coronavirus the peripheral airways, i.e. the bronchioles) they take root and then multiply.
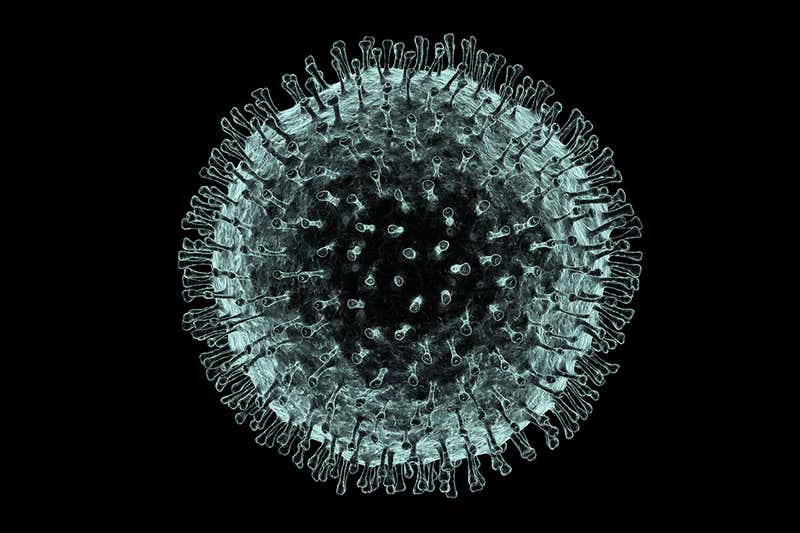
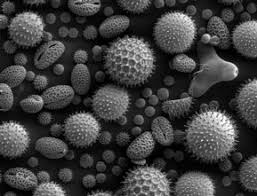
Coronavirus
Pollen eines Haselnussstrauches
Pollen from a peanut bush

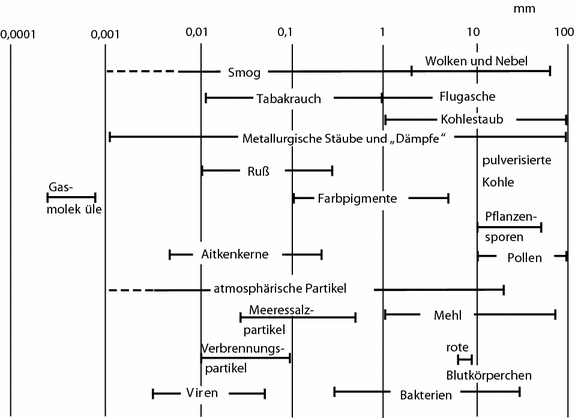
Their dimensions are also comparable to those of smoke particles, they get to the alveoli and are then inhaled and exhaled. This is the difference to droplet particles, which having a diameter about 60 times higher, are picked up by the upper respiratory tracts.
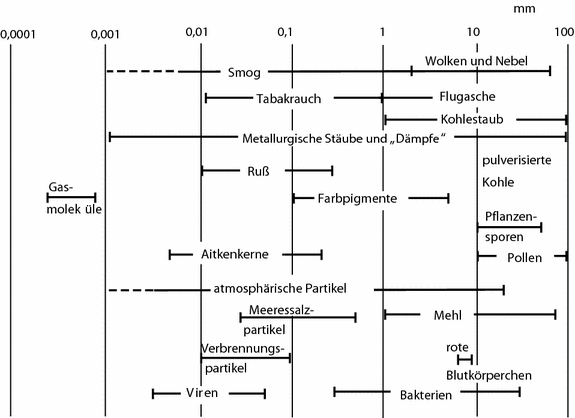

The Coronavirus’ gateway to the body and its replication finally take place at the level of the peripheral airways (bronchioles), where they induce an inflammatory response mediated by antibodies similar to allergic asthma. This is why the severity of the disease does not primarily depend on the damage caused to the organism by the virus, but on the damage caused by the immune system to the organism (4), which is why cortisone was the first choice drug in aggravated cases at the beginning of the pandemic.

The modes of falling ill with coronavirus are comparable to those of falling ill from passive smoking. Coming into contact with people who transmit coronavirus is the same as coming into contact with smokers. The harmful agent is inhaled in the same way and the dangerous load for the organism only takes place in closed, badly ventilated environments.

In this respect the Robert Koch Institute has confirmed that transmission of the virus in the open is highly improbable (RKI).
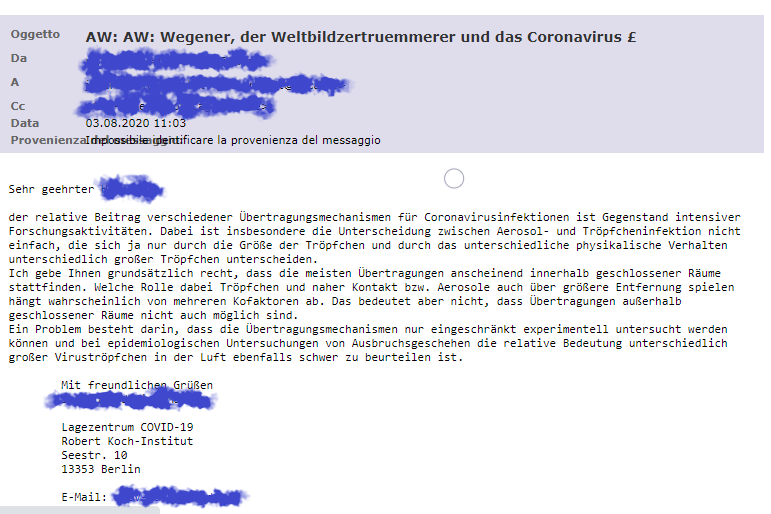
  1. Masks are very dangerous because they greatly reduce the aeration of the lungs.

Once respiratory system patients were sent to the mountains or the sea to exhale the unhealthy air and inhale clean air, whereas now they are provided with masks and the exhaled air (which contains a high number of viruses during the infectious phase) cannot disperse in the open air but is retained by the mask and subsequently inhaled.


“Put on your costume”

In this respect masks oblige people to infect themselves more and more (as if one smoked under the mask), condemning them to an increasingly serious risk to their health and producing severely ill patients.

And so, breath by breath, people reduce their chances of survival. HOORAY FOR MEDICINE!

Unfortunately medicine is not a science, but an opinion. Day by day many opinions (political, economic, populist etc.) interfere on the orientation of medicine, also with compliant experts in the medical sphere. In arithmetic, (which is a science) one and one makes two (1+1=2), in medicine (which is an opinion) 1+1 does not always make 2, it eventually makes 3, 4 or 18, 24, maybe better 42-2, according to the current opinion.
With the current government measures we are actually forced to take refuge in closed places, right where we get infected and then we are forced to endure serious or very serious harm caused by the obligation for masks. We are taken right there, young and old, where we don’t want to end up, in the arms of the angel of death.

APPENDIX:

Ceterum censeo, Cartaginem esse delendam, thus Cato, the Censor finished each of his speeches at the Senate.

In this sense this contribution ends with: Ceterum Censeo, that the situation is not of a medical but a political/economic nature, public good and health have nothing to do with it, common people are nothing but cannon fodder:

  1. Because there is a daily organized disinformation of the population regarding mortality, lethality, contagiousness index, deceased, newly infected, re-infection, asymptomatic, healthy carriers, positives. The latter are pursued with all the means at the disposal of the state, as if they were criminals. But this hunt makes no sense, as the contagiousness index is completely unrelated to mortality, as shown by the statistics issued by the Italian government on 4/11/20 (A).
casi covid
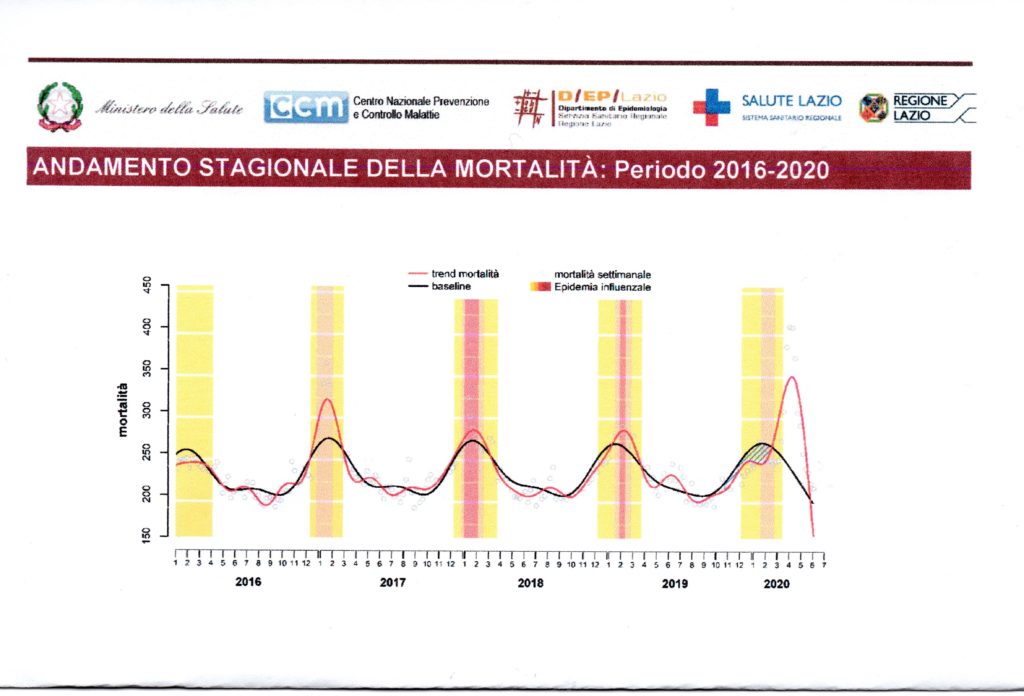
  1. Because disastrous news is broadcast every day regarding the pandemic, even though this year (e.g. in Italy, in Germany the relevant data is not available) there has not been a statistically significant rise in mortality compared to the period 2015-2019. From May-August there was even a reduction in mortality compared to the five previous years by 1.6% (ISTAT Report, National Institute of Statistics 22/10/2020 (Table 1)(B).
  2. Because the statistics released by the media predict a significant increase in deaths from coronavirus with distressing forecasts for the future, (“soon over 1,000 deaths a day”), even though the lethality of Coronavirus is estimated at 0.14% against the 0.10 of common ‘flu (WHO 14/10/20)(C). Possibly because even patients without laboratory confirmation are included in the deaths with only a suspected diagnosis (as a result of medical or epidemiological evaluation) (Report of the National Health Insitute (ISS), n.49/2020,8/6/20, note 1)(D), or because the statistical elaboration was carried out on limited groups of patients (4942 of 31.573 deaths from Coronavirus to 25/05/2020), or because inappropriate terms of definition were used. The term “directly responsible for death”, means that the death would not have beenverified if the SARS-CoV-2 infection had not intervened, although often overlapping other pre-existing conditions, and their complications. (Report from the “National Institute of Statistics on16/7/2020: Impact of the Covid-19 epidemic on mortality: Causes of death of SARS-CoV-2 positives, note 2)(E).
  3. At the moment almost all the hospitals in almost all Europe are nearly full of Coronavirus patients, even though current mortality is much lower than in the spring. Also the capacity of hospital beds for coronavirus patients has increased since then. This could serve to recover the deficit of hospitals caused by the dramatic reduction in hospital admissions due to the pandemic (the deficit in the first 4 months in Italy is 3.5 bilions of Euro: Report ALTEMS) (F). In this way the Budget can be met, so as not to remain insolvent. (“Coronavirus rettet die Kliniken, aber die Pleitegefahr bleibt hoch” = the coronavirus crisis saves the hospitals, but the risk of bankruptcy remains high. Das Handelsblatt ) (G). In Germany the state pays the hospitals about 700 euro for every unoccupied bed, to keep it free for the eventual second wave of the pandemic. All this because direct subsidies at EU level are no longer permitted. If someone cannot uphold their financial obligations, they have to declare insolvency, a disaster for public healthcare.
  4. Because in March wide-spectrum trials of antiviral drugs like Remdesivir (Solodarity etc.) were authorized globally, where the control group did not receive any specific pharmacological drug, which actually should have been cortisone. In their wake the same useless medicines have been tested almost everywhere.
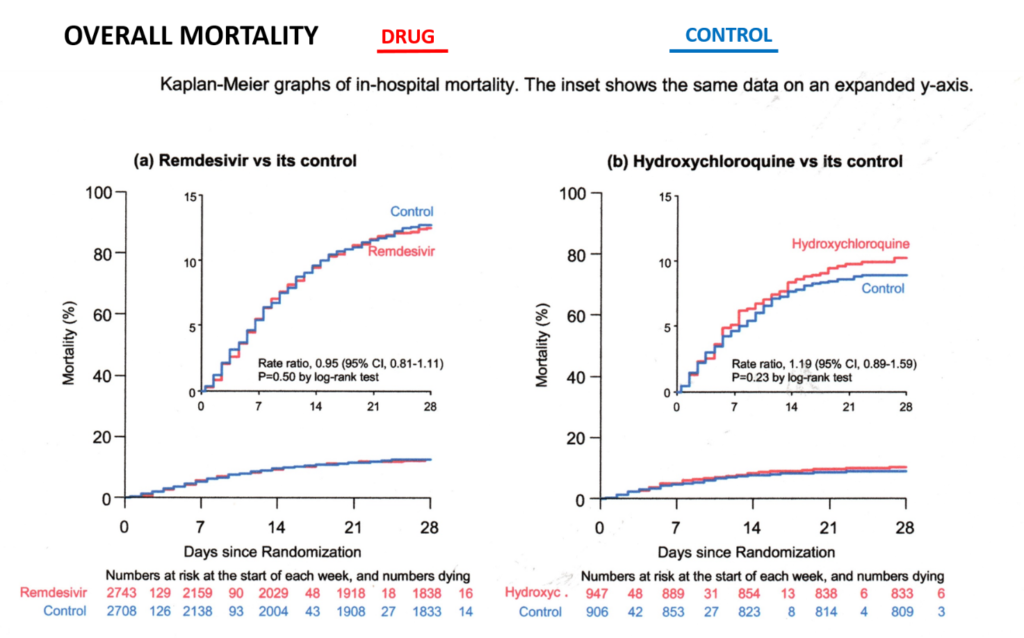
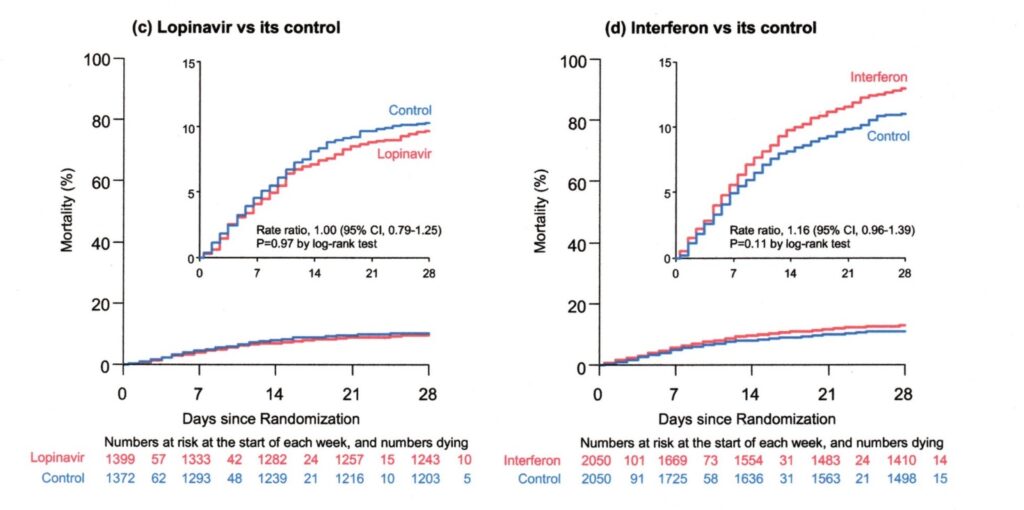
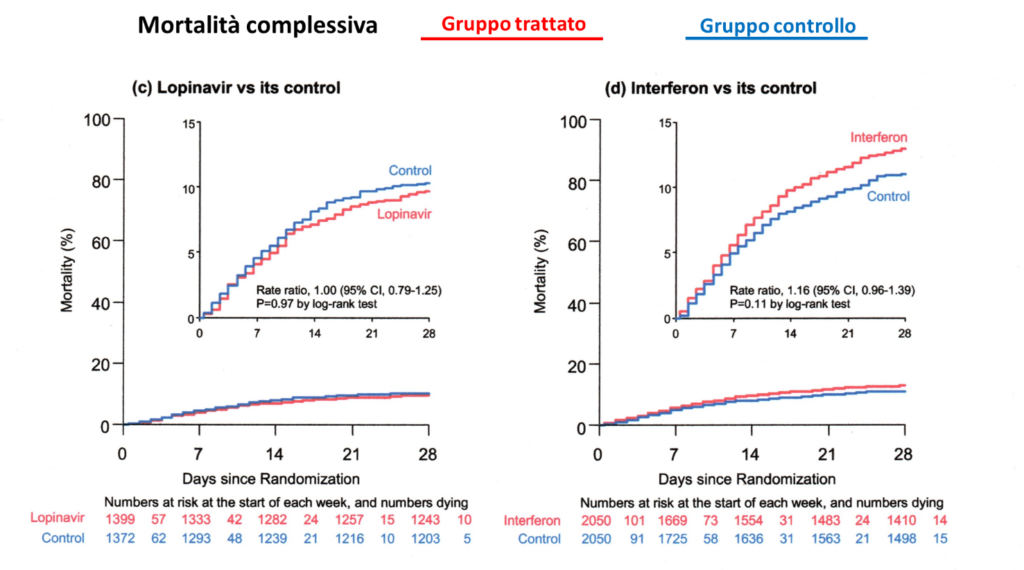
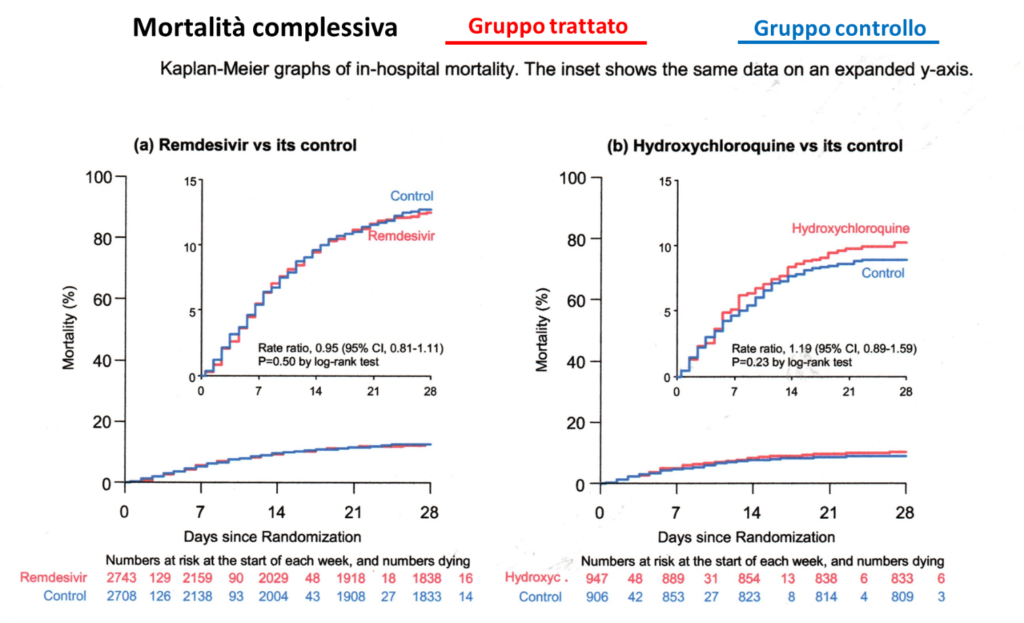
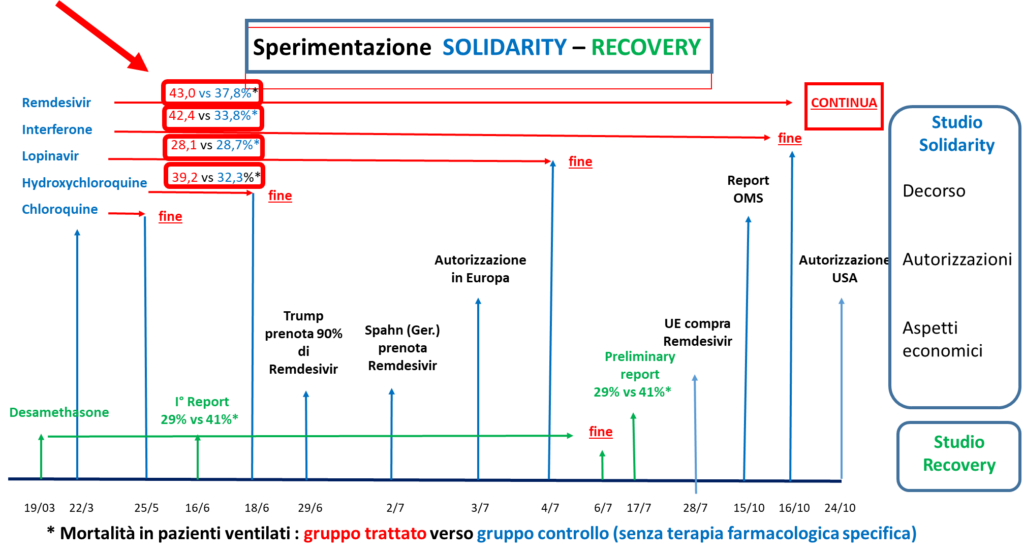
  5. Because they insisted on testing for many months to ascertain whether the therapy was beneficial, which was already evident after a month (statistical elaboration through the Kaplan Meier 28 Day Mortality method, Table 2) (H). In fact mortality was superior to the control group. In these trials mortality for ventilated patients was 41% (Solidarity study), while with the cortisone therapy it was 29% (Recovery Study) (I). All these useless pharmaceutical trials have caused the death of thousands of people under the pretext of scientific research. And all this in general without having requested and obtained the informed consent from the patients/relatives, because a European legal provision exonerated the experimenter from this obligation for the Covid emergency (European Medicines Agency etc.) (J), seriously infringing the fundamental constitutional rights of every citizen. No patient or relative would have signed an informed consent stating that half the patients were left with no treatment but only the placebo.
  6. Because the European governments were advised to authorize the use of Remdesivir on 3 July, (knowing that it was useless) and because they were advised to get huge supplies of this drug (Table 3), which promptly took place (European Commission) (K).
  7. Because a worldwide race for vaccines began, unsafe both for the abbreviated test procedure due to the Covid emergency, but also for the strong economic interests (the over 160 centers in the world have been sponsored on average with 200 Million Euro). There is also hardly any state control of the trials. The sponsor (i.e. who pays for the trials with a high compensation to the hospitals) and the ethical commission are responsible for controlling the correct conduct of the trial itself (the dream of every student: I write the assignment, I mark it and give it a grade). Vaccination during an ongoing epidemic can also trigger serious side effects like the narcolepsy during the vaccination against swine ‘flu in 2009.
  8. In this epidemic too the political reaction proved completely exaggerated. The EU (to name some countries) spent about 1.3 billion in England and over 700 million in France for a vaccine for a ‘flu which had caused only 2,900 deaths in Europe compared to the European average of 40,000 to 220,000 a year from common ‘flu (EC debate 7/3/2011) (L). In 2009 Transparency International (The Global Coalition against Corruption) had already criticized the financing of the European Medicines  Agency (EMA) for two thirds of the Pharmaceutical Industry (M). The European Court of Auditors later confirmed this conflict of interest (Press release ECA/12/39 on 11/10/2012) (N).Whoever performs vaccination during an ongoing epidemic commits a grave error
  9. Because the “VirologicalScience” does not admit to having wrongly assessed the means of transmission of the Coronavirus (O). It is in the same situation as Gottlob Frege (1902), who in the end discovered important errors in his research defining the bases of mathematics (note 3).
  10. Because there is a relentlessness towards children, our future, considering them global super-spreaders.

TRAUMATIZING CHILDREN CONSTITUTES A CRIME AGAINST “HUMANITY”

The answer my friends, is blowing in the wind, the answer is blowing in the wind.

Appendix

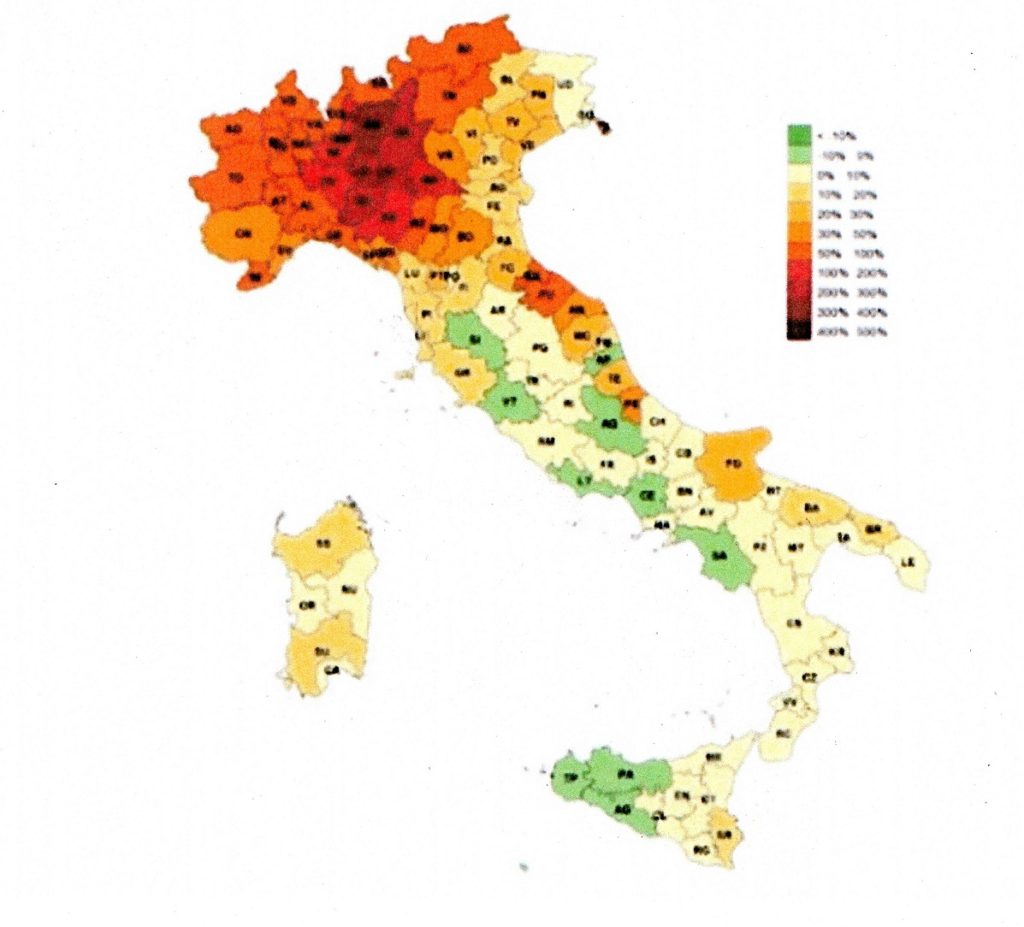
Table 1) – Percentage variation in deaths in 2020 compared to the 2015-2019 average, by region, distribution and month.
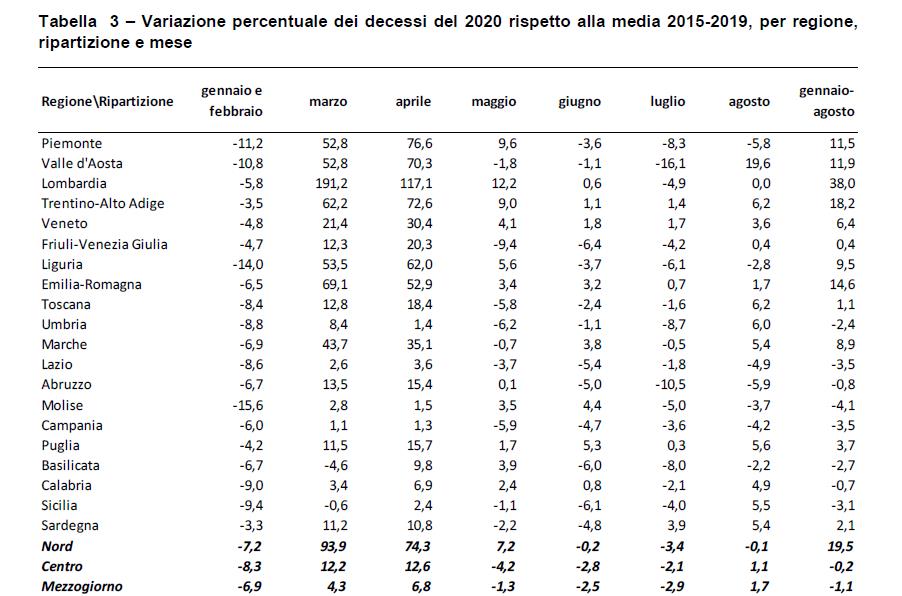
Report ISTAT, National Institute of Statistics, 22/10/2020

Table 2)

Statistical elaboration: Kaplan Meier 28 day risks (mortality), available monthly from April on the WHO site. The monthly results have clearly shown the inefficacy of the antiviral drugs involved, hence the study should have been interrupted much sooner. Each month of delay causes unnecessary deaths.
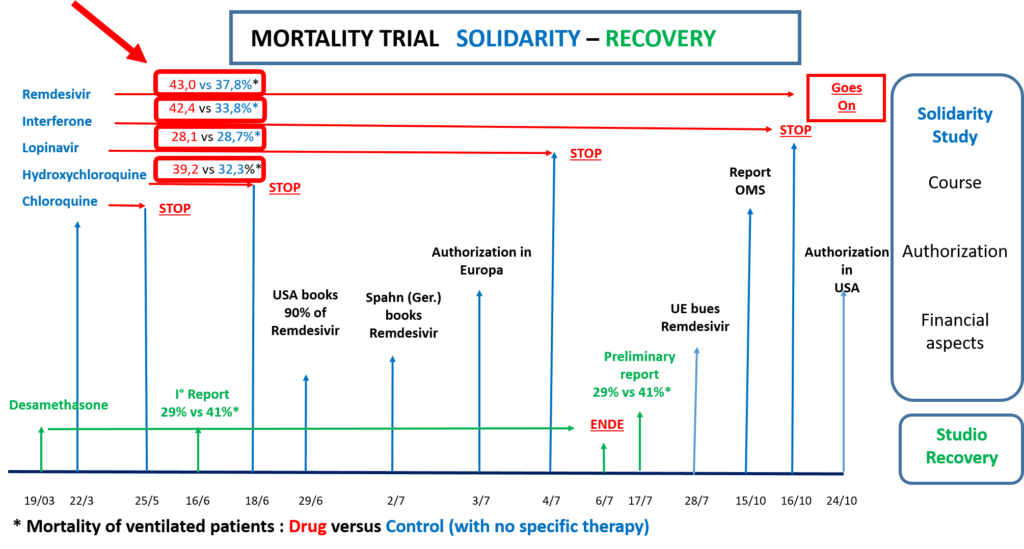
Timeline of the experiments (Mortality PV* = Ventilated Patients, control** = with no specific therapy)

19/03    Recovery trial begins

22/3       Solidarity (S) trial begins                                              monthly report of results

25/5       Chloroquine leaves Solidarity   

16/6       1st Recovery Report                                     Mortality PV*   Cortisone: 29%, control** 41%

18/6       Hydroxychloroquine leaves Solidarity:  Mortality PV*  H.chloroquine 39.2%, control** 32.3%

29/6       USA books 90% of the Remdesivir resources

2/7         Germany (Spahn) books large reserves of Remdesivir

3/7         UE authorizes the use of Remdesivir

4/7         Lopinavir leaves Solidarity                          Mortality PV*   Lopinavir 28.1%, control** 28.7%

6/7         Recovery trial ends

17/7       Recovery trial Report                                    Mortality PV*   Cortisone 29%,                 control** 41%

28/7       UE buys Remdesivir

15/10    WHO Report                                     Mortality PV*   Remdesivir 43.0%, control** 37.8%

24/10    USA authorizes the use of Remdesivir

Note 1) “National Health Institute, Report n.49/2020, 8/6/2020: “COVID-19: Interim Report on the  definition, certification and classification of the causes of death”

According to this report the patients included in the 33.000 until 7/6/20 are composed as follows:

  1. Suspected case (without laboratory investigation: Author’s note)
  2. Someone with acute respiratory infection and with no other etiology, which completely explains the clinical presentation and with a travel or residence history with transmission of the virus.
  3. Someone with any acute respiratory Infection who has been in contact with a probable or confirmed case of Covid.
  4. Probable case: suspected case whose SARS-CoV-2 test result is doubtful or inconclusive (i.e. despite negative test the diagnosis is confirmed: Author’s note)
  5. Confirmed case. Case with laboratory confirmation independently of signs and clinical symptoms.

Note 2) “National Institute of Statistics” ISTAT Report from 16/7/20: “Impact of the Covid-19 epidemic on Mortality: Causes of death of positive deceased from SARS-CoV-2”

The report includes 4,942 statements of death submitted to the National Institute of Health with confirmed SARS-CoV infection. This constitutes only 15.6% of the reported cases until 25/5/20 out of a total of 31.573 deaths. Therefore the remaining cases are suspected or probable cases (i.e.with no laboratory diagnosis).

The statistical elaboration of this small group of patients has emphasised that: “Covid-19 is the directly responsibile cause of death in 89% of deaths of people positive to SARS-CoV-2”, a statement which is repeated daily like a prayer wheel.

Definition of directly responsibile for death: death is caused directly by Covid-19, when death would not have been verified, if the SARS-Cov-2 infection had not intervened (although often overlapping other pre-existing illnesses and their complications).

Note 3) The virological community should publicly release the same declaration as Frege on 16/6/1902 (modified by vaso di pandora): “Hardly anything more unwelcome can befall a scientific writer (virological community) than that one of the foundations of his edifice be shaken after the work (program for the “fight” against the pandemic) is finished. This is the position into which I was put (still Frege) by a letter from Mr Betrand Russell (Wegener der Weltbildzertruemmerer), as the printing of this volume (Public Measures against the Pandemic) was nearing completion.

Bibliography

  1. European Centre for Disease Prevention and Control: Using the masks in the Community. https://www.ecdc.europa.eu/en/publications-data/using-face-masks-community-reducing-covid-19-transmission
  2. Ministero della Salute Italiano: Covid-19: Situazione in Italia al 4/11/2020. http://www.salute.gov.it/portale/nuovocoronavirus/dettaglioContenutiNuovoCoronavirus.jsp?area=nuovoCoronavirus&id
  3. Vaso di Pandora: Aerosol als der einzig relevanter Uebertragungsweg des Coronavirus: epidemiologische Analyse, 29/05/2020. https://www.vasodipandora.net/2020/05/29/aerosol-als-der-einzig-relevanter-uebertragungsweg-des-coronavirus-epidemiologische-analyse/

Vaso di Pandora: L’aerosol quale unica via rilevante di trasmissione del coronavirus: evidenze epidemiologiche, 24/05/2020. https://www.vasodipandora.net/2020/05/24/laerosol-quale-unica-via-rilevante-di-trasmissione-del-coronavirus-evidenze-epidemiologiche/

Vaso di Pandora: Considerazioni generali sul coronavirus, 25/05/2020- https://www.vasodipandora.net/2020/05/25/considerazioni-generali-sul-coronavirus/

A) Ministero della Salute Italiano: Covid-19: Situazione in Italia al 4/11/2020. http://www.salute.gov.it/portale/nuovocoronavirus/dettaglioContenutiNuovoCoronavirus.jsp?area=nuovoCoronavirus&id

B) Istituto Nazionale di Statistica; decessi e cause di morte. 4/11/2020 https://www.istat.it/it/archivio/240401#:~:text=Decessi%20e%20cause%20di%20morte%3A%20cosa%20produce%20l%E2%80%99Istat,da%20fonte%20anagrafica%2C%20con%20cadenza%20mensile%20ed%20annuale.

C) John P. A. Ioannidis, Bulletin of the WHO: Infection fatality rate of COVID-19 inferred from seroprevalence data, 14/10/2020. https://www.who.int/bulletin/online_first/BLT.20.265892.pdf

D) Istituto Superiore della Sanità (ISS): COVID-19: rapporto ad interim su definizione, certificazione e classificazione delle cause di morte, n.49/2020. 8/6/20

E) Istituto di Statistica Italiana: Impatto dell’epidemia COVID-19 sulla mortalità: cause di morte nei deceduti positivi a SARS-COV-2, https://www.istat.it/it/archivio/245573

F) Alta Scuola di Economia e Management dei Sistemi Sanitari (ALTEMS): Interim analysis sull’impatto economico per l’Ssn del Covid-19, 28/05/2020, https://altems.unicatt.it/altems-flash%20report%20altems.pdf

G) Das Handelsblatt: Coronakrise rettet die Kliniken – aber die Pleitegefahr bleibt hoch, 18/06/2020, https://www.handelsblatt.com/technik/medizin/krankenhausmarkt-coronakrise-rettet-die-kliniken-aber-die-pleitegefahr-bleibt-hoch/25928050.html?ticket=ST-8782875-ukG7jD77bEeYcW6Kezpt-ap2

H) WHO Solidarity trial consortium: Repurposed antiviral drugs foe COVID-19 – interim WHO SOLIDARITY trial results, 15/10/2020, https://www.medrxiv.org/content/10.1101/2020.10.15.20209817v1.full.pdf

I) The Recovery Collaborative Group: Dexamethasone in hospitalized Patients with Covid-19 – Preliminary Report, 17/07/2020, https://www.nejm.org/doi/full/10.1056/NEJMoa2021436

J) European Medicines Agency: Guidance on the Management of Clinical Trials during the COVID-19 (Coronavirus) pandemic, 28/4/20, https://ec.europa.eu/health/sites/health/files/files/eudralex/vol-10/guidanceclinicaltrials_covid19_en.pdf

K) European Commission: European Commission secures EU access to Remdesivir for treatment of COVID-19, 29/07/2020, https://ec.europa.eu/commission/presscorner/detail/en/ip_20_1416

L) Plenardebatte 07/03/2011 – Umgang mit der H1N1 – Grippe (Europaeische Union), https://europarl.europa.eu/sides/getDoc.do?pubRef=-//EP//TEXT+CRE+20110307+ITEM-023+DOC+XML+V0//DE

M) Transparency Intenational: Transparency Deutschland fordert Aufarbeitung des Schweinegrippen-Fehlalarms, 07/10/2011, https://www.transparency.org/en/press/20111007-schweinegrippe

N) Europaeischer Rechungshof: Interessenkonflikte wurden von den ausgewaehlten Agenturen nicht angmessen gehamdhabt, 11/10/2020. https://ec.europa.eu/commission/presscorner/detail/de/ECA_12_39

O) Gottlob Frege: Eine Einfuehrung in sein Werk, Walter de Gruyter – Berlin – New York 1989, https://books.google.it/books?id=du2_q1PRTRAC&pg=PP5&source=kp_read_button&redir_esc=y#v=onepage&q&f=false

Die Vier Ausscheidungswege und das Coronavirus

oder: Die Medizin ist keine Wissenschaft, sondern eine Meinung.

Die Maskenpflicht wird zur Zeit als eine der wichtigsten Massnahmen hinsichtlich der Coronapandemie angesehen. Diese wird, wie viele andere diesbezuegliche Massnahmen, nur aus populistischen politischen Gruenden vorgeschrieben, hat allerdings keinerlei Einfluss auf die Uebertragung des Virus, sondern stellt sogar eine Gefaehrdung fuer deren Traeger dar  (1)(European Center for Disease Prevention and Controll, 8/4/2020). Von dieser Tatsache wird abgelenkt, indem absichtlich eine grosse Verwirrung zwischen Erkrankten, Verstorbenen, Positiven, Spreadern etc, erzeugt wird.

Letztendlich wurde in ganz Europa die Reproduktionszahl (Robert Koch Insitut) als Richter ueber Gut und Boese eingefuehrt, der die Laender teilt, aufgrundi ihrer guten und boesen Buerger. Letztere werden ohne Gnade bestraft, ohne jeglicher wissenschaftlicher Basis und statistisch gesehen vollstaendig unhaltbar. Somit wird als eines der Hauptziele in der „Bekaempfung des Coronavirus“ die Jagd nach „Positiven“ mit allen dem Staat verfuegbaren Mitteln (Corona-Apps) in Gang gesetzt. Die „Aufgespuerten“ und Ihre Angehoerigen werden unter Hausarrest und oeffentlich an den Pranger gestellt, als waeren sie Verbrecher.

Dies alles wird durchgesetzt, obwohl keinerlei Zusammenhang zwischen neuen Positiven und Todesfaellen besteht, wie von den neuesten Statistiken aus Italien belegt wird (2) (Ministero della Salute).

casi covid
Kurven – gelb: Neuinfektionen, gruen: Geheilte, grau: Todesfaelle

ABER WESHALB MACHEN DIE MASKEN KEINEN SINN?

Ich will es hier mit ein paar einfachen Worten erklaeren:

Unser Koerper verfuegt ueber vier Ausscheidungswege schaedlicher Substanzen, ueber Niere (Urin), Darm (Kot), Haut (Transpiration) und ueber die Lunge (Respiration). Letztliche, bedeutend fuer die Uebertragung des Coronavirus, muss einerseits den Gasaustausch Sauerstoff – Kohlendioxid gewaehrleisten, aber ebenfalls die Belueftung der Atemwege, der Nasennebenhoehlen und des Mittelohres.

Wenn dieser Weg unterbrochen oder reduziert wird (das gleiche gilt fuer die anderen drei Wege), vergiftet sich der Koerper und wird eventuell irreversibel geschaedigt.

Und jetzt kommen wir zu den Gesichtsmasken.

  1. Die Gesichtsmasken schuetzen in keinster Weise vor einer Infektion mit Coronavirus, deren Uebertagung nur ueber Aerosol (3) und nicht ueber Troepfchen oder Schmierinfektion erfolgt.

Die Coronaviren sind von ihrem Aussehen her nicht von verschiedenen Pollen zu unterscheiden, sie sind nur um ein vielfaches kleiner (ein Wunder der Natur). Sie verbreiten sich wie diese, schwebend in der Luft und werden von ihr fortgetragen. Fallen sie auf einen fruchtbaren Boden (fuer die Coronaviren die peripheren Luftwege: die Bronchiolen) so koennen sie sich dann weitervermehren.

Coronavirus
Pollen eines Haselnussstrauches

Die Groesse des Coronavirus ist vergleichbar mit denen der Teilchen des Zigarettenrauches, erreichen die  Lungenblaeschen und werden somit ein und ausgeatmet. Dies im Unterschied zu den Teilchen des Droplet , die einen ungefaehr 60 mal groesseren Durchesser haben und deshalb von den oberen Luftwegen abgefangen werden.

Die Eintrittspforte in den menschlichen Koerper fuer das Coronavirus und seine Vervielfaeltigung erfolgt in den tieferen Luftwegen (Brochiolen), wobei es eine antikoerpervermittelte Immunantwort (vergleichbar mit dem allergischem Astma), hervorruft. Somit ist die Schwere der Krankheit nicht durch die Schaeden aufgrund des Virus sondern aufgrund unserer Immunabwehr bedingt, deswegen war seit Anfang der Coronapandemie das    Kortison    das Arzneimittel erster Wahl im fortgeschrittenem Stadium.

Man erkrankt an Coronavirus wie an Passivrauch durch Kontakt mit Personen die Coronavirus/Tabakrauch ausscheiden. Die Aufnahme einer gefaehrlichen Gesamtmenge erfolgt nur in geschlossenen, schlecht geluefteten Raeumen.Diesbezueglich hat auch das Robert Koch Insitut (Deutschland) bestaetigt, dass “die meisten Uebertragungen anscheinend innerhalb geschlossener Raeume stattfinden“.

  1. Die Gesichtsmasken sind schwer gesundheitsschaedlich, da sie die Belueftung der Lungen verringern.

Bis vor kurzem wurden die Lungenkranken ins Sanatorium in die Berge oder ans Meer geschickt , jetzt werden im Gegenteil Masken verordnet, wodurch sich die Ausatemluft (die eine hohe Konzentration an  Coronaviren enthaelt), nicht in der freien Luft verteilen kann, sondern von den Masken blockiert wieder eingeatmet wird.

Somit zwingen die Masken die Personen dazu, sich selber immer mehr zu infizieren (als rauche einer unter einer Maske), und werden somit zu einem immer groesseren Risiko fuer ihre Gesundheit verurteilt. Das gleiche gilt auch fuer Kinder, die normalerweise nicht an Coronavirus erkranken, aber durch die Masken einen eventuellen toedlichen Krankheitverlauf aufweisen koennen.

Und so verringern die Personen, Atemzug um Atemzug, ihre Ueberlebenschance. ES LEBE DIE MEDIZIN!Die Medizin ist leider keine Wissenschaft, sondern eine Meinung. Tag fuer Tag wirken unzaehlige Meinungen (politischer, oekonomischer, mediatischer Natur) auf die Ausrichtung der Medizin ein, auch aufgrund von „gefaelligen“ medizinischen Experten. In der Arithmetik, (eine Wissenschaft) ergibt eins plus eins zwei (1+1-2). In der Medizin (eine Meinung) ergibt 1+1 nicht immer 2, ergibt gegebenenfalls 3,4 oder 18,24, vielleicht sogar 42-2, je nach der vorherrschenden Meinung.

Mit den derzeitigen Massnahmen der Regierungen werden wir gezwungen, uns in geschlossene Raeumlichkeiten zurueckzuziehen, gerade dahin, wo wir uns infizieren. Ausserdem werden wir dazu gezwungen, schwere und schwerste Schaeden durch die Maskenpflicht zu erleiden.

Wir werden geradezu dahin getrieben, jung und alt, wohin wir nie wollten: in die Arme des Todesengels.

ANHANG:

Ceterum censeo, Cartaginem esse delendam.

So endete Cato Major jede seiner Reden im Senat,

und in diesem Sinne endet dieser Beitrag: Ceterum censeo, dass die derzeitige Lage in keinster Weise medizinischer Natur ist, sondern nur politischer und oekonomischer. Das oeffentliche Wohl und die Gesundheit hat damit nichts zu tun, der gemeine Buerger ist nur Kannonenfutter.

  1. Weswegen erfolgt taeglich oeffentliche organisierte Fehlinformation der Bevoelkerung bezueglich Mortalitaet, Laetalitaet, Erkrankten, Reproduktionszahl, Toten, Neuinfektionen, Reinfektionen, und Asymptomatischen. Letztere werden mittlerweile mit allen dem Staat verfuegbaren Mitteln verfolgt, als waeren sie Verbrecher, obwohl alle Statistiken aufzeigen, dass keinerlei Zusammenhang zwischen neuen Positiven und Todesfaellen besteht (A).
casi covid
Kurven – gelb: Neuinfektionen, gruen: Geheilte, grau: Todesfaelle
  1. Weswegen werden jeden Tag neue Schreckensnachrichten hinsichtlich der Coronapandemie verbreitet, obwohl in diesem Jahr (hier Italien als Beispiel, in Deutschland sind diesbezuegliche Daten allgemein nicht abrufbar) kein statistisch signifikanter Anstieg der Sterblichkeit hinsichtlich des Zeitraumes 2015-19 zu verzeichnen ist. Im Zeitraum Mai – August 2020 wurde eine Verringerung der Sterblichkeit in Italien bezueglich 2015-2019 um 1,6% verzeichnet (Report ISTAT. Istituto Nazionale di Statistica, 22/10/2020, (Tabella 1)(B).
  2. Weswegen sehen die “medialen “ Statistiken einen betraechtlichen Anstieg der „Coronatoten“ vor mit duesteren Zukunftsprognosen (bald mehr als 1000 Tode pro Tag), obwohl die Coronafallsterblichkeit nur 0.2% betraegt (World Health Organisation, 14/10/2020)(C). Liegt dies eventuell auch daran, dass auch Patienten mit reiner Verdachtsdiagnose (aufgrund medizinischer oder epidemilogischer Einschaetzung), ohne labortechnischem Nachweis mit eingeschlossen werden (Fussnote 1, Report des Istituto Superiore della Sanità (ISS), n.49/2020, 8/6/2020)(D)? Oder koennte dies durch die statistische Aufarbeitungen von nur begrenzten Patientenkollektiven (4942 von insgesamt 31.573 Coronatoten) oder auch durch die unzutreffende Definitionen verursacht werden. Unter „Direkt verantwortlich fuer den Todesfall“ wird definiert, dass der Tod nicht eingetreten waere, wenn die SARS-CoV-2 Infektion nicht erfolgt waere, obwohl haeufig Vorerkrankungen oder ihre Komplikationen gleichzeitig vorhanden sind“ (Report des „Istituto Nazionale di Statistica“ (ISTAT) del 16/7/2020:.”Impatto dell’Epidemia Covid-19 sulla Mortalità: Cause di morte dei deceduti positivi a SARS-Cov-2”, Fussnote 2)(E)?
  3. Weswegen sind zur Zeit in ganz Europa die Krankenhaeuser aufgrund Coronapatienten fast ausgelastet, obwohl die Sterblichkeit zur Zeit nur ungefaehr 10-20% derer des Fruehjahres betraegt? Ausserdem wurden mittlerweile die Kapazitaeten von Krankenhausplaetzen fuer Coronapatienten erhoeht. Dient dies dazu, das Defizit der Krankenhaeuser aufgrund der dramatische Unterbelegung infolge der Coronaepidemie auszugleichen (Defizit in den ersten 4 Monaten in Italien von 3.5 Miliarden Report ALTEMS Alta Scuola di Economia e Management dei Sistemi Sanitari) (F). So kann das jaehrliche Budget erreicht werden, um nicht insolvent zu werden („Coronakrise rettet die Kliniken – aber die Pleitegefahr bleibt hoch Das Handelsblatt, Germania) (G). In Deutschland zahlt mittlerweile der Staat fuer jedes unbelegte Krankenhausbett 700 Euro taeglich „in Erwartung der zweiten Coronawelle“. All dies, da direkte Subventionen in der UE nicht mehr erlaubt sind. Kann jemand seinen finanziellen Verpflichtungen nicht nachkommen, muss er Konkurs anmelden, undenkbar fuer das Gesundheitssystem, ein Supergau.
  4. Weswegen wurden im Maerz klinische Studien auf weltweiter Ebene bezueglich der Wirksamkeit antiviraler Medikamenten wie Remdesivi (Solidarity etc.) autorisiert, bei der die Kontrollgruppe keiner spezifischen pharmakologischen Therapie unterzogen wurde, die jedoch das Kortison haette sein muessen. Diese Studien hatten weltweit unzaehlige aehnliche Studien mit denselben unnuetzen Medikamenten als Folge, mit denselben enttaeuschenden Ergebnissen
  5. Weswegen fuehrte man diese Studien fuer viele Monate weiter, obwohl bereits nach einem Monat deutlich war (statistische Auswertung: Kaplan Meier 28 Day Mortality, Tabelle 2) (H), dass die Medikamente nicht nur voellig unwirksam waren, sondern sogar eine hoehere Sterberate als bei der Kontrollgruppe ohne jeglicher speziefischer Therapie verursachten. Die Sterblichkeit von ventilierten Patienten lag bei 41% (Trial Solidarity), waehren die von ventilierten Patienten unter Kortisongabe (Trail Recovery) bei 29% lag (I). Diese pharmakologischen Studien haben somit den Tod von vielen Menschen unter dem Vorwand der wissenschaftlichen Forschung verursacht, und all dies ohne grossteils eine Pazienteneinwilligung fuer diese Studien einzuholen. Die Gesetzgebung in Europa befreite die „Sponsoren“ aufgrund des Covidnotfalles davon, unter schwerwiegenster Verletzung der Rechte der Erkrankten (European Medicines Agency et al.) (J). Kein Patient/Angehoeriger haette jemals eine Einwilligung unterschrieben mit der Erklaerung, dass die Haelfte der Studienteilnehmer ohne spezifischer medizinischer Therapie gelassen wurde, sondern nur mit einem Placebo.
  6. Weswegen wurden den Regierungen empfohlen, Remdesivir am 3. Juli in Europa zuzulassen, obwohl seit Monaten deren Unwirksamkeit nachgewiesen war, und weswegen wurden Vorraete dieses unnuetzen Medikamentes in grossen Mengen von Europa (European Commission) (K) erworben (Tabelle 3).
  7. Weswegen wurde das Rennen um die Impfung auf der ganzen Welt eroeffnet, fuer eine Impfung die unsicher ist, sowohl aufgrund der abgekuerzten Versuchsdauer wegen der Notfallsituation Coronavirus, als auch wegen immensen finanziellen Interessen (die mehr als 160 Zentren, sind im Durchschnitt mit 200 Millionen Euro gesponsort). Hier fehlt fast vollstaendig eine staatliche Kontrolle der Studienablaeufe. Der Sponsor (derjenige der die Krankenhaeuser mit grosser finanzieller Zuwendung die Studien durchfuehren laest) ist selbst, mit der Ethikkommission, dafuer verantwortlich, die eigenen Studienvorgaben zu erfuellen. (ein Traum eines jeden Schuelers: Ich schreibe meine Schulaufgabe, ich korrigiere sie selbst und benote mich dann selbst). Ausserdem fuehrt eine Impfung waehrend einer Epidemie zu schweren Zwischenfaellen wie die Narkolepsie aufgrund der Schweinegrippeimpfung 2009. Auch bei dieser Epidemie war die politische Antwort vollkommen uebertrieben. Es wurden von der Europaeischen Union (um nur ein paar Laender zu nennen) ungefaehr 1.3 Miliarden in England, mehr als 700 Millionen in Frankreich fuer diese Impfung ausgegeben, obwohl nur 2900 Todesfaellen in Europa am Ende zu registrieren war. Im Vergleich versterben an der saisonalen Grippe in Europa jaehrlich 40.000-220.000 Menschen (siehe Plenardebatte 7/3/2011 der Europaeischen Union) (L). Trasparency International (The Global Coalition against Corruption) hatte bereits 2009 die Finanzierung der Europaeischen Arzneimittelargentur (EMA) zu fast zwei Dritteln durch die pharmazeutische Industrie kritisiert (M). Der Europaeische Rechnungshof hat diese Interessenkonflikte oeffentlich bestaetigt (Pressemitteilung ECA/12/39 vom 11/10/2012) (N). Wer eine Impfung waehrend einer laufenden Epidemie durchfuehrt, beginnt einen medizinischen Fehler.
  8. Weswegen gibt die “Virologische Wissenschaft” nicht zu, dass sie den Uebertragungsweg des Coronavirus falsch beurteilt hat (“Seit man begonnen hat, einfachste Behauptungen zu beweisen, erweisen sich viele als falsch: Zitat Russel Bertrand). Sie ist in der gleichen Lage von Gottlob Frege (O), der beim Versuch, die Basis der Mathematik zu definieren, auf eigene fundamentale Fehler gestossen war (Fussnote 3)
  9. Weswegen werden die Kinder, ins Visier genommen, unsere Zukunft, als waeren sie diejenigen, die die Welt infizierten.

KINDER ZU TRAUMATISIEREN IST EIN VERBRECHEN GEGEN DIE MENSCHLICHKEIT.

The answer my friends, is blowing in the wind, the answer is blowing in the wind.

Tabelle 1

Tabelle 2

Statistik: Kaplan Meier 28 day mortality (seit April monatlich abrufbar ueber die Home page WHO).Die Ergebnisse haben monatlich die Unwirksamkeit der angewandten Arzneimittel dargelegt. Die Studie haette baldmoeglichst abgebrochen werden muessen, um weiter Todesfaelle“ im Namen der wissenschaftlichen Forschung“ zu vermeiden.

Tabelle 3

Chronologie der klinischen Studien: Versuchsgruppe, Kontrollgruppe (ohne spezifischer pharmakologischer Therapie), Sterblichkeit von ventilierten Patienten in %

19/03    Anfang des Trial Recovery:  ( Kortison)

22/3       Anfang des Trial Solidarity:  (Chloroquine, Hydrochloroquine, Lopinavir, Interferone, Remdesivir)

25/5       Ende Chloroquine im Trial Solidarity      

16/6       I° Report Recovery                                                       

Kortisone:          29%,     Kontrollgruppe                41%

18/6       Ende Hydroxychloroquine im Trial Solidarity:   

  H.chloroquine   39.2%, Kontrollguppe. 32.3%

29/6       USA bestellen 90% von Remdesivir vor

2/7         Deutschland bestellt Remdesivir vor

3/7         UE laesst Remdesivir in Europa zu

4/7         Ende Lopinavir im Trial Solidarity                           

  Lopinavir             28.1%, Kontrollgruppe                28.7%

6/7         Ende Trial Recovery      

17/7       Report Trial Recovery                                                  

Cortisone            29%,      Kontrollgruppe                41%

28/7       UE erwirbt Remdesivir

15/10    Report WHO                                                                  

  Remdesivir         43.0%,                 Kontrollgruppe 37.8%

16/10    Ende Interferone im Trial Solidarity                       

Interferone       42.4%,                 Kontrollgruppe 33.8%

24/10    USA laesst Remdesivir zu

Fussnote 1)

Report des “Istituto Superiore della Sanità”, n.49/2020, 8/6/2020: “COVID-19: rapporto ad interim  su definizione, certificazione e classificazione delle cause di morte”

Gemaess diesem Report setzt sich das Patientengut der statistischen Covid-2 Erfassung in Italien (mehr als 33.000 Todesfaelle bis zum 7/6/20), wie folgt zusammen:

1)            Verdachtsfaelle (ohne Labornachweis, Note des Autors)

a) Patienten mit akuter respiratorischer Infektion, keiner anderen Aethiologie, Reise oder Wohnort in einem Gebiet mit lokaler Uebertragungsgefahr.

b) Patienten mit jeglichem akutem respiratorischem Infekt, die in den vorhergegangenen 15 Tagen mit einem moeglichem oder bestaetigten Coronaerkrankten in Kontakt gekommen sind.

c) Patienten mit akutem respiratorischem Infekt, der eine Krankenhauseinweisung erfordert (keine anderen Aethiologie).

(Dies ohne Labornachweis)

2)    Wahrscheinliche Faelle: Verdachtsfaelle mit fraglichen oder unschluessige Ergebnissen des Labortest SARS-Cov-2

3)    Sichere Faelle: Personen mit positivem Labortest unabhaengig von klinischen Krankheitszeichen oder Symptomen.

Fussnote 2)

Report des „Istituto Nazionale di Statistica“ (ISTAT) del 16/7/2020:.”Impatto dell’Epidemia Covid-19 sulla Mortalità: Cause di morte dei deceduti positivi a SARS-Cov-2”

Der Report umfasst 4942 Todesmeldungen von Patienten mit nachgewiesener Covid-19 Infektion, die der Staatlichen Institution „Istitut Superiore della Sanità“ zugesandt wurden. Sie stellen nur 15.6% der Gesamttodesfaelle (31.573 zum 25/5/2020) dar. Somit sind wahrscheinlich der Rest (26.631) Verdachtsfaelle oder wahrscheinliche Faelle (alle also ohne positivem Labortest).

Die Auswertung dieses kleinen Patientenkollektives ergab folgendes Ergebnis:

COVID-19 ist im 89% der Todesfaelle direkt fuer den Tod von SARS-CoV-2 positiven Patienten verantwortlich.

Unter dem Begriff: direkt verantwortlich versteht man, dass der Tod nicht erfolgt waere, wenn die SARS-CoV-2 Infektion nicht eingetreten waere, obwohl haeufig Vorerkrankungen oder ihre Komplikationen gleichzeitig vorhanden sind.

Fussnote 3)

Die Virologische Gesellschaft muesste mehr oder weniger dieselbe oeffentliche Erklaerung abgeben wie Frege am 16/06/1902 (modifiziert nach Vaso di Pandora): „Einem wissenschaftlichen Schriftsteller (der virologischen Gemeinschaft) kann kaum etwas Unerwünschteres begegnen, als daß ihm nach Vollendung einer Arbeit (Progamm fuer die Bekaempfung der Pandemie), eine der Grundlagen seines Baues erschüttert wird. — In diese Lage wurde ich (Frege) durch einen Brief des Herrn Bertrand Russell (Wegener, der Weltbildzertruemmerer) versetzt, als der Druck dieses Bandes (Oeffentliche Massnahmen zur Bekaempfung der Pandemie) sich seinem Ende näherte”.

Bibliografia

  1. European Centre for Disease Prevention and Control: Using the masks in the Community. https://www.ecdc.europa.eu/en/publications-data/using-face-masks-community-reducing-covid-19-transmission
  2. Ministero della Salute Italiano: Covid-19: Situazione in Italia al 4/11/2020. http://www.salute.gov.it/portale/nuovocoronavirus/dettaglioContenutiNuovoCoronavirus.jsp?area=nuovoCoronavirus&id
  3. Vaso di Pandora: Aerosol als der einzig relevanter Uebertragungsweg des Coronavirus: epidemiologische Analyse, 29/05/2020. https://www.vasodipandora.net/2020/05/29/aerosol-als-der-einzig-relevanter-uebertragungsweg-des-coronavirus-epidemiologische-analyse/

Vaso di Pandora: L’aerosol quale unica via rilevante di trasmissione del coronavirus: evidenze epidemiologiche, 24/05/2020. https://www.vasodipandora.net/2020/05/24/laerosol-quale-unica-via-rilevante-di-trasmissione-del-coronavirus-evidenze-epidemiologiche/

Vaso di Pandora: Considerazioni generali sul coronavirus, 25/05/2020- https://www.vasodipandora.net/2020/05/25/considerazioni-generali-sul-coronavirus/

A) Ministero della Salute Italiano: Covid-19: Situazione in Italia al 4/11/2020. http://www.salute.gov.it/portale/nuovocoronavirus/dettaglioContenutiNuovoCoronavirus.jsp?area=nuovoCoronavirus&id

B) Istituto Nazionale di Statistica; decessi e cause di morte. 4/11/2020 https://www.istat.it/it/archivio/240401#:~:text=Decessi%20e%20cause%20di%20morte%3A%20cosa%20produce%20l%E2%80%99Istat,da%20fonte%20anagrafica%2C%20con%20cadenza%20mensile%20ed%20annuale.

C) John P. A. Ioannidis, Bulletin of the WHO: Infection fatality rate of COVID-19 inferred from seroprevalence data, 14/10/2020. https://www.who.int/bulletin/online_first/BLT.20.265892.pdf

D) Istituto Superiore della Sanità (ISS): COVID-19: rapporto ad interim su definizione, certificazione e classificazione delle cause di morte, n.49/2020. 8/6/20

E) Istituto di Statistica Italiana: Impatto dell’epidemia COVID-19 sulla mortalità: cause di morte nei deceduti positivi a SARS-COV-2, https://www.istat.it/it/archivio/245573

F) Alta Scuola di Economia e Management dei Sistemi Sanitari (ALTEMS): Interim analysis sull’impatto economico per l’Ssn del Covid-19, 28/05/2020, https://altems.unicatt.it/altems-flash%20report%20altems.pdf

G) Das Handelsblatt: Coronakrise rettet die Kliniken – aber die Pleitegefahr bleibt hoch, 18/06/2020, https://www.handelsblatt.com/technik/medizin/krankenhausmarkt-coronakrise-rettet-die-kliniken-aber-die-pleitegefahr-bleibt-hoch/25928050.html?ticket=ST-8782875-ukG7jD77bEeYcW6Kezpt-ap2

H) WHO Solidarity trial consortium: Repurposed antiviral drugs foe COVID-19 – interim WHO SOLIDARITY trial results, 15/10/2020, https://www.medrxiv.org/content/10.1101/2020.10.15.20209817v1.full.pdf

I) The Recovery Collaborative Group: Dexamethasone in hospitalized Patients with Covid-19 – Preliminary Report, 17/07/2020, https://www.nejm.org/doi/full/10.1056/NEJMoa2021436

J) European Medicines Agency: Guidance on the Management of Clinical Trials during the COVID-19 (Coronavirus) pandemic, 28/4/20, https://ec.europa.eu/health/sites/health/files/files/eudralex/vol-10/guidanceclinicaltrials_covid19_en.pdf

K) European Commission: European Commission secures EU access to Remdesivir for treatment of COVID-19, 29/07/2020, https://ec.europa.eu/commission/presscorner/detail/en/ip_20_1416

L) Plenardebatte 07/03/2011 – Umgang mit der H1N1 – Grippe (Europaeische Union), https://europarl.europa.eu/sides/getDoc.do?pubRef=-//EP//TEXT+CRE+20110307+ITEM-023+DOC+XML+V0//DE

M) Transparency Intenational: Transparency Deutschland fordert Aufarbeitung des Schweinegrippen-Fehlalarms, 07/10/2011, https://www.transparency.org/en/press/20111007-schweinegrippe

N) Europaeischer Rechungshof: Interessenkonflikte wurden von den ausgewaehlten Agenturen nicht angmessen gehamdhabt, 11/10/2020. https://ec.europa.eu/commission/presscorner/detail/de/ECA_12_39

O) Gottlob Frege: Eine Einfuehrung in sein Werk, Walter de Gruyter – Berlin – New York 1989, https://books.google.it/books?id=du2_q1PRTRAC&pg=PP5&source=kp_read_button&redir_esc=y#v=onepage&q&f=false


Le quattro vie di eliminazione ed il coronavirus

Oppure : La medicina non è una scienza, ma una opinione

L’obbligo delle mascherine viene considerata una delle misure più efficaci per contrastare la pandemia da coronavirus. Tale misura viene imposta, come tante altre, solo per motivi politici populistici e risulta non solo completamente inefficace per quanto riguarda una riduzione della trasmissione del virus, ma costituisce addirittura un pericolo serio per la salute di chiunque indossi la mascherina (1) (European Centre for Disease Prevention and Control 2020). Da tale problematica si devia creando volutamente una grande confusione fra malati, morti, sieropositivi, portatori sani, asintomatici, positivi ecc.

Alla fine fu introdotto l’indice di contagiosità (Robert Koch Institut) quale sommo giudice sul bene e sul male, che divide i paesi arbitrariamente in zone dei bravi e dei cattivi cittadini, quest’ultimi da punire senza pietà. Tutto questo avviene senza alcuna base scientifica ed è statisticamente improponibile, ma la caccia ai positivi con tutti i mezzi disponibili allo stato (App immune ecc.) è diventata una delle “armi principali nella battaglia contro il Coronavirus”. I positivi poi scoperti ed i loro familiari vengono messi agli arresti domiciliari ed alla gogna, come fossero dei criminali.

Questa caccia però non ha alcun senso, essendo l’indice di contagiosità completamente scollegato dalla mortalità, come evidenziato dalla statistica emessa dal Ministero della Salute Italiano il 4/11/20 (2).

casi covid
Curva    -gialla: attualmente positivi, verde: guariti, grigio: decessi

MA PERCHE’ LE MASCHERINE NON VANNO BENE?

Ve lo spiego in poche parole.

Il nostro corpo dispone di quattro vie di eliminazione di sostanze nocive: apparato urinario (urina), apparato digestivo (feci), pelle (traspirazione) ed i polmoni (respirazione). Quest’ultima via, che è importante per quanto riguarda la trasmissione del coronavirus, deve garantire sia lo scambio di ossigeno/anidride carbonica che l’aerazione delle vie respiratorie, dei seni nasali e paranasali e dell’orecchio medio.

Interrompendo o riducendo questa via, il che vale anche per tutte le altre vie, il corpo si intossica progressivamente e viene danneggiato anche in maniera irreversibile.

Ed ora arriviamo alle mascherine:

  1. Le mascherine non proteggono in alcun misura dalla infezione da coronavirus essendo la via di trasmissione esclusivamente quella aerea tramite aerosol (3) e non quella per via goccioline oppure attraverso contatto.

I Coronavirus hanno una forma sovrapponibile a quella di vari pollini (una meraviglia della natura) ma sono solo molto più piccoli e si trasmettono come quelli, sospesi e trasportati dall’ aria. Se arrivano ad un terreno fertile (per i coronavirus le vie aeree periferiche, cioè i bronchioli) attecchiscono ed in seguito avviene la moltiplicazione.

Coronavirus
Polline del cespuglio di Nocciolo

Le loro dimensioni poi sono sovrapponibili a quelle delle particelle del fumo, arrivano ai alveoli e vengono allora ispirati ed espirati. Questo è la differenza rispetto alle particelle del Droplet, che avendo un diametro circa 60 volte superiore, vengono captate dalle vie respiratorie superiori.

La porta di ingresso nel corpo del Coronavirus e la sua replicazione avviene alla fine a livello delle vie aeree periferiche (bronchioli), inducendo lì una risposta infiammatoria mediata da anticorpi paragonabile all’asma allergico. Per questo motivo la gravità della malattia non dipende primariamente dai danni causati dall’virus all’organismo, ma dai danni causati dalle difese immunitarie all’organismo (4), per cui il cortisone era dall’inizio della pandemia il farmaco di prima scelta nei casi aggravati.

La modalità di ammalarsi da coronavirus e paragonabile a quella di ammalarsi da fumo passivo. Venendo a contatto con persone che emettono il coronavirus succede lo stesso come venendo a contatto con persone fumatori. Si ispira l’agente nocivo nella stessa maniera e la carica pericolosa per l’organismo avviene solo in ambienti chiusi, mal aerati. A tale proposito anche il Robert Koch Institut ha confermato, che una trasmissione del virus all’aperto è molto improbabile (RKI).

  1. Le mascherine sono molto dannose, perché riducono notevolmente l’aerazione dei polmoni.

Una volta i malati del apparato respiratorio venivano mandati in montagna oppure al mare per espirare l’aria insana e ispirare aria pulita, ora invece vengono forniti di mascherine per cui l’aria espirata (che contiene un elevato numero di virus durante la fase infettiva) non si può disperdere nell’aria aperta ma viene trattenuta dalla mascherina e successivamente inspirata.

In tale senso le mascherine obbligano le persone, di autoinfettarsi sempre di più (come se uno fumasse sotto la mascherina), condannandole ad un rischio sempre più grave per la loro salute e producendo malati gravi.

Così, respiro per respiro, le persone riducono la loro probabilità di sopravvivenza. EVVIVA LA MEDICINA! Purtroppo la medicina non è una scienza, ma una opinione. Giorno per giorno interferiscono tanti opinioni (politici, economici, populistici ecc.) sull’orientamento della medicina, anche a causa di esperti della sfera medica compiacenti. Nell’aritmetica, (che è una scienza) uno più uno fa due (1+1=2), nella medicina (che è una opinione) 1+1 non fa sempre 2, fa eventualmente 3,4 oppure 18, 24, magari meglio 42-2, a secondo l’opinione vigente.

Con le attuali misure dei governi veniamo proprio costretti di rifugiarci nei posti chiusi, proprio là, dove ci infettiamo e poi veniamo costretti di subire delle gravi oppure gravissimi danni causati dall’obbligo delle mascherine. Veniamo portati proprio lì, giovani e vecchi, dove non vogliamo finire, nelle braccia dell’angelo della morte.

APPENDICE:

Ceterum censeo, Cartaginem esse delendam, così finiva Catone, il Censore, ogni suo intervento al senato.

In tale senso finisce questo contributo con: Ceterum Censeo, che la situazione non è di natura medica ma di natura politica/economica, il bene e la salute pubblica non c’entra niente, le persone comuni non sono altro che carne da cannone:

casi covid
Curva    -gialla: attualmente positivi, verde: guariti, grigio: decessi
  1. Perché avviene giornalmente una disinformazione organizzata della popolazione riguardante mortalità, letalità, indice di contagiosità, deceduti, infetti nuovi, reinfezione, asintomatici, portatori sani, positivi. Quest’ultimi vengono inseguiti con tutti i mezzi a disposizione dello stato, come se fossero dei delinquenti. Ma questa caccia non ha senso, essendo l’indice di contagiosità completamente scollegato dalla mortalità, come evidenziato dalla statistica emessa dal governo italiano il 4/11/20 (A).
  2. Perché vengono diffuse ogni giorno notizie disastrose per quanto riguarda la pandemia, nonostante che in questo anno (Italia come esempio, in Germania non sono disponibili i dati a tale proposito) non c’è stato un aumento statisticamente significativo della mortalità rispetto al periodo 2015-2019. Nel periodo maggio-agosto ci fu addirittura una riduzione della mortalità rispetto ai cinque anni precedenti del 1.6% (Report ISTAT, Istituto Nazionale di Statistica, 22/10/2020 (Tabella 1)(B).
  3. Perché le statistiche diffuse dalle media prevedono un aumento considerevole dei decessi da coronavirus con previsioni angoscianti per il futuro, (“fra poco più di 1000 morti al giorno”), nonostante la letalità da Coronavirus viene stimato del 0.14% contro il 0.10 della influenza comune (WHO 14/10/20)(C). Questo forse perché pazienti anche senza conferma di laboratorio, vengono inclusi nella mortalità con la sola diagnosi di sospetto (a causa di valutazione medica o epidemilogica) (Rapporto del Istituto Superiore della Sanità (ISS), n.49/2020,8/6/20, nota 1)(D), oppure perché la elaborazione statistica fu eseguita su gruppi limitati di pazienti (4942 di 31.573 morti per Coronavirus al 25/05/2020), oppure perché sono stati utilizzati termini di definizioni inadatte. Sotto il termine “direttamente responsabile per il decesso”, si intende, che il decesso non si sarebbe verificato se l’infezione da SARS-CoV-2 non fosse intervenuta, seppure spesso sovrapposto ad altre malattie preesistenti, e dalle sue complicanze (Report del “Istituto Nazionale di Statistica” ISTAT) del16/7/2020: Impatto dell’epidemia Covid-19 sulla mortalità: Cause di morte dei positivi a SARS-CoV-2, nota 2)(E).
  4. Attualmente quasi tutti i ospedali in quasi tutto l’Europa sono pressoché pieni di pazienti di Coronavirus, nonostante la mortalità attuale è molto inferiore rispetto alla primavera. Inoltre nel frattempo fu aumentata la capacità dei letti ospedalieri per pazienti da Coronavirus,. Potrebbe servire questo, per recuperare il deficit dei ospedali causato dalla drammatica riduzione dei accessi ai ospedali a causa della pandemia (il deficit nei primi 4 mesi in Italia è di 3.5: Report ALTEMS Alta Scuola di Economia e Management dei sistemi Sanitari) (F). In tale maniera si può raggiungere il Budget, per non rimanere insolvente (“Coronavirus rettet die Kliniken, aber die Pleitegefahr bleibt hoch” = la crisi da coronavirus salva gli ospedali, ma il rischio di fallimento rimane alto. Das Handelsblatt ) (G). In Germania lo stato paga ai ospedali circa 700 euro per ogni letto non occupato con la motivazione, di tenerlo libero per l’attesa della eventuale seconda onda della pandemia. Tutto questo perché sovvenzioni diretti a livello della Communita europea non sono più permessi. Se qualcuno non può rispettare i suoi obblighi finanziari, deve dichiarare insolvenza, un disastro per la sanità pubblica.
  5. Perché venivano autorizzate a marzo sperimentazioni a largo spettro a livello mondiale di farmaci antivirali quali Remdesivir (Solodarity ecc.) con il gruppo di controllo, che non otteneva nessuna terapia farmacologica specifica, che invece doveva essere il cortisone. Nella loro scia sono state sperimentate quasi ovunque le stesse medicine inutili.
  6. Perché si insisteva nella sperimentazione per molti mesi per appurare che la terapia aveva alcun beneficio, il che era già evidente dopo un mese (elaborazione statistica tramite metodo Kaplan Meier 28 Day Mortality, Tabella 2) (H). Anzi la mortalità era addirittura superiore al gruppo di controllo. La mortalità in questi studi per pazienti ventilati era del 41% (studio Solidarity), mentre quella con la terapia con cortisone era del 29% (Studio Recovery) (I). Tutte queste sperimentazioni farmaceutiche inutili hanno causato la morte di migliaia di persone con il pretesto della ricerca scientifica. E tutto questo in linea di massima senza aver chiesto ed ottenuto il consenso informato da parte dei pazienti/parenti, perché un a disposizione legge in Europa esonerava per l’emergenza Covid lo sperimentatore da questo obbligo (European Medicines Agency ecc.) (J), ledendo in maniera grave i diritti costituzionali fondamentali di ogni cittadino. Nessuno paziente oppure parente avrebbe firmato un consenso informato contenente l’affermazione, che la metà dei malati venivano lasciati senza terapia di riferimento ma solo con il placebo.
  7. Perché fu consigliato ai governi europei di autorizzare l’utilizzo del Remdesivir il 3 Luglio, (sapendo che era inutile e perché fu consigliato a loro di fare approvvigionamenti ingenti di tale farmaco (Tabella 3),.come prontamente avvenuto (European Commission) (K).
  8. Perché fu iniziata una corsa ai vaccini in tutto il mondo, insicuro sia per la procedura di sperimentazione abbreviata a causa della emergenza Covid, ma pure per i forti interessi economici (i oltre 160 centri nel mondo sono sponsorizzati mediamente con 200 Milione di Euro). Inoltre manca pressoché completamente un controllo statale dei studi. Lo sponsor (cioè chi paga la sperimentazione con un forte compenso ai ospedali) e la commissione etica sono i responsabili per controllare il corretto svolgimento della sperimentazione stessa (il sogno di ognun studente: io scrivo il compito, il lo correggo ed io do il voto). Inoltre la vaccinazione durante una epidemia in corso può comportare dei seri effetti collaterali come la narcolessia durante la vaccinazione contro l’influenza suina del 2009. Anche in questa epidemia la reazione politica si era dimostrato completamento esagerata. Sono stati spesi dall’Unione Europea (per nominare alcuni paesi) circa 1.3 miliardi in Inghilterra e oltre 700 milioni in Francia per il vaccino per una influenza, che aveva causato in Europa solo 2900 decessi rispetto alla media in Europa della influenza comune di 40.000 a 220.000 l’anno (dibattito Comunione Europea del 7/3/2011) (L). Trasparency International (The Global Coalition against Corruption) aveva già nel 2009 criticato il finanziamento della Agenzia Europea del Farmaco (EMA) per i due terzi dalla Industria Farmaceutica (M). In seguito la Corte dei Conti Europea ha confermato questo conflitto d’interesse (Comunicazione stampa ECA/12/39 del 11/10/2012) (N). Chi effettua una vaccinazione durante una epidemia in corso commette un grave errore
  9. Perché la “Scienza Virologica” non ammette, di aver valutato in maniera sbagliata la via di trasmissione del Coronavirus (O). Essa trova nella stessa situazione come Gottlob Frege (1902), che nella sua ricerca, di definire le basi della matematica, alla fine ha riscontrato dei errori importanti (nota 3).
  10. Perché c’è un accanimento contro i bambini, il nostro futuro, considerandoli untori del mondo .

TRAUMATIZZARE I BAMBINI COSTITUISCE UN CRIMINE CONTRO ‘UMANITA’

The answer my friends, is blowing in the wind, the answer is blowing in the wind.

Appendice

Tabella 1

Report ISTAT, Istituto Nazionale di Statistica, 22/10/2020

Tabella 2)

Elaborazione statistica: Kaplan Meier 28 day risks (mortality), da aprile mensilmente consultabile presso il sito OMS. I risultati mensilmente hanno chiaramente dimostrato l’inefficacia dei farmaci antivirali impegnati, per cui lo studio doveva essere interrotto molto prima. Ogni mese di ritardo è causa di decessi evitabili.

Tabella 3

Cronologia delle sperimentazioni: Gruppo trattato, gruppo controllo (senza terapia farmacologica specifica), mortalità di pazienti ventilati in %

19/03    Inizio trial Recovery        Cortisone

22/3       Inizio trial Solidarity (S)   Chloroquine, Hydroxychloroquine, Lopinavir, Interferone, Remdesivir

25/5       Chloroquine esce da Solidarity 

16/6       I° Report Recovery         Cortisone:          29%,      controllo             41%

18/6       Hydroxychloroquine esce da Solidarity                

H.chloroquine   39.2%,                 controllo             32.3%

29/6       USA prenotano 90% delle risorse Remdesivir

2/7         Germania prenota Remdesivir

3/7         Autorizzazione Unione Europea (UE)

4/7         Lopinavir esce da Solidarity                                      

  Lopinavir             28.1%, controllo            28.7%

6/7         Fine trial Recovery         

17/7       Report trial Recovery                                                  

  Cortisone            29%,      controllo             41%

28/7       UE compra Remdesivir

15/10    Report WHO                  Remdesivir         43.0%, controllo             37.8%

16/10    Interferone esce da Solidarity                                

  Interferone       42.4%, controllo             33.8%

24/10    Autorizzazione USA

Nota 1) Report dell’”Istituto Superiore della Sanità, n.49/2020, 8/6/2020: “COVID-19: Rapporto ad interim su definizione, certificazione e classificazione delle cause di morte”

Secondo questo rapporto i pazienti inclusi nei 33.000 fino al 7/6/20 si compongono come segue:

  1. Caso sospetto (senza indagine di laboratorio: Nota dell’autore)
    • Persona con infezione respiratoria acuta e senza un’altra eziologia, che spieghi completamente la presentazione clinica e con storia di viaggi o residenza con trasmissione del virus
    • Persona con qualsiasi infezione respiratoria acuta che è stato in contatto con caso probabile o confermato Covid.
  2. Caso probabile: caso sospetto il cui risultato al test per SARS-CoV-2 è dubbio o inconcludente (cioè nonnostante test negativo viene confermato la diagnosi: Nota dell’autore)
  3. Caso confermato. Caso con conferma di laboratorio indipendentemente dai segni e dai sintomi clinici.

Nota 2) Report dell’”Istituto Nazionale di Statistica” ISTAT del 16/7/20: “Impatto dell’epidemia Covid-19 sulla Mortalità: Causa di morte dei deceduti positivi al SARS-CoV-2”

Il rapporto include 4942 schede di morte pervenute all’ Istituto superiore della Sanità con infezione da SARS-CoV confermati. Questo costituisce solo il 15.6% dei casi segnalati fino al 25/5/20 su un totale di 31.573 deceduti. Il rimanenti casi sono allora casi sospetti o probabili (cioè senza diagnosi di laboratorio.)

La elaborazione statistica di questo esiguo gruppo di paziente ha evidenziato che: “Covid-19 è la causa direttamente responsabile della morte nell’89% dei decessi di persone positive al SARS-CoV-2”, una affermazione, che viene giornalmente ripetuta come una ruota della preghiera.

Definizione direttamente responsabile per la morte: la morte è causata direttamente da Covid-19, quando il decesso non si sarebbe verificato, se l’infezione da SARS-Cov-2 non fosse intervenuta (seppure spesso sovrapposto ad altre malattie preesistenti e delle sue complicanze).

Nota 3) La comunità virologica dovrebbe rilasciare pubblicamente la stessa dichiarazione come Frege il 16/6/1902 (modificato da vaso di pandora): Ad un autore scientifico (comunità virologica) difficilmente puo accadere una cosa piu indesiderata dopo la il completamento della sua opera (programma per la “lotta” contro la pandemia), che una base della sua costruzione viene scosso. In questa situazione mi sono trovato (sempre Frege) a causa della lettera del Sig. Bertrand Russell (Wegener der Weltbildzertruemmerer), quando la stampa del mio libro (Misure Pubbliche contro la Pandemia) giungeva alla fine.

Bibliografia

  1. European Centre for Disease Prevention and Control: Using the masks in the Community. https://www.ecdc.europa.eu/en/publications-data/using-face-masks-community-reducing-covid-19-transmission
  2. Ministero della Salute Italiano: Covid-19: Situazione in Italia al 4/11/2020. http://www.salute.gov.it/portale/nuovocoronavirus/dettaglioContenutiNuovoCoronavirus.jsp?area=nuovoCoronavirus&id
  3. Vaso di Pandora: Aerosol als der einzig relevanter Uebertragungsweg des Coronavirus: epidemiologische Analyse, 29/05/2020. https://www.vasodipandora.net/2020/05/29/aerosol-als-der-einzig-relevanter-uebertragungsweg-des-coronavirus-epidemiologische-analyse/

Vaso di Pandora: L’aerosol quale unica via rilevante di trasmissione del coronavirus: evidenze epidemiologiche, 24/05/2020. https://www.vasodipandora.net/2020/05/24/laerosol-quale-unica-via-rilevante-di-trasmissione-del-coronavirus-evidenze-epidemiologiche/

Vaso di Pandora: Considerazioni generali sul coronavirus, 25/05/2020- https://www.vasodipandora.net/2020/05/25/considerazioni-generali-sul-coronavirus/

A) Ministero della Salute Italiano: Covid-19: Situazione in Italia al 4/11/2020. http://www.salute.gov.it/portale/nuovocoronavirus/dettaglioContenutiNuovoCoronavirus.jsp?area=nuovoCoronavirus&id

B) Istituto Nazionale di Statistica; decessi e cause di morte. 4/11/2020 https://www.istat.it/it/archivio/240401#:~:text=Decessi%20e%20cause%20di%20morte%3A%20cosa%20produce%20l%E2%80%99Istat,da%20fonte%20anagrafica%2C%20con%20cadenza%20mensile%20ed%20annuale.

C) John P. A. Ioannidis, Bulletin of the WHO: Infection fatality rate of COVID-19 inferred from seroprevalence data, 14/10/2020. https://www.who.int/bulletin/online_first/BLT.20.265892.pdf

D) Istituto Superiore della Sanità (ISS): COVID-19: rapporto ad interim su definizione, certificazione e classificazione delle cause di morte, n.49/2020. 8/6/20

E) Istituto di Statistica Italiana: Impatto dell’epidemia COVID-19 sulla mortalità: cause di morte nei deceduti positivi a SARS-COV-2, https://www.istat.it/it/archivio/245573

F) Alta Scuola di Economia e Management dei Sistemi Sanitari (ALTEMS): Interim analysis sull’impatto economico per l’Ssn del Covid-19, 28/05/2020, https://altems.unicatt.it/altems-flash%20report%20altems.pdf

G) Das Handelsblatt: Coronakrise rettet die Kliniken – aber die Pleitegefahr bleibt hoch, 18/06/2020, https://www.handelsblatt.com/technik/medizin/krankenhausmarkt-coronakrise-rettet-die-kliniken-aber-die-pleitegefahr-bleibt-hoch/25928050.html?ticket=ST-8782875-ukG7jD77bEeYcW6Kezpt-ap2

H) WHO Solidarity trial consortium: Repurposed antiviral drugs foe COVID-19 – interim WHO SOLIDARITY trial results, 15/10/2020, https://www.medrxiv.org/content/10.1101/2020.10.15.20209817v1.full.pdf

I) The Recovery Collaborative Group: Dexamethasone in hospitalized Patients with Covid-19 – Preliminary Report, 17/07/2020, https://www.nejm.org/doi/full/10.1056/NEJMoa2021436

J) European Medicines Agency: Guidance on the Management of Clinical Trials during the COVID-19 (Coronavirus) pandemic, 28/4/20, https://ec.europa.eu/health/sites/health/files/files/eudralex/vol-10/guidanceclinicaltrials_covid19_en.pdf

K) European Commission: European Commission secures EU access to Remdesivir for treatment of COVID-19, 29/07/2020, https://ec.europa.eu/commission/presscorner/detail/en/ip_20_1416

L) Plenardebatte 07/03/2011 – Umgang mit der H1N1 – Grippe (Europaeische Union), https://europarl.europa.eu/sides/getDoc.do?pubRef=-//EP//TEXT+CRE+20110307+ITEM-023+DOC+XML+V0//DE

M) Transparency Intenational: Transparency Deutschland fordert Aufarbeitung des Schweinegrippen-Fehlalarms, 07/10/2011, https://www.transparency.org/en/press/20111007-schweinegrippe

N) Europaeischer Rechungshof: Interessenkonflikte wurden von den ausgewaehlten Agenturen nicht angmessen gehamdhabt, 11/10/2020. https://ec.europa.eu/commission/presscorner/detail/de/ECA_12_39

O) Gottlob Frege: Eine Einfuehrung in sein Werk, Walter de Gruyter – Berlin – New York 1989, https://books.google.it/books?id=du2_q1PRTRAC&pg=PP5&source=kp_read_button&redir_esc=y#v=onepage&q&f=false


CORONAVIRUS: HISTORY AND PRESENT

CORONAVIRUS: VERGANGENHEIT UND GEGENWART

CORONAVIRUS: PASSATO E PRESENTE


As far back as 1982 the coronavirus was described explicitly in a book on microbiology-


Bereits 1982 wurde das Coronavirus ausfuehrlich in einem Lehrbuch fuer Mikrobiologie beschrieben


Già in un libro del 1982 di microbiologia il coronavirus fu descritto in maniera esplicita.

Prof. GIUSEPPE COCUZZA
Head of the Institute of Microbiology, University of Catania
COURSE IN MICROBIOLOGY
SECOND EDITION 1982
Edited by Prof. G. NICOLETTI AND Prof. A. CASTRO
 
CHAPTER XX
CORONAVIRUS
The term coronavirus has been adopted to generically define a recently isolated group of viruses which present common characteristics and in particular the presence around the virion of large petaloid projections which form a characteristic corona (hence the name of the group).
The coronaviruses contain NRA as nucleic acid not well defined in structure and conformation. They have a probably helicoidal symmetry and the nucleocapsid is coated in lipoprotein.
The complete virion is round with slight pleiomorphism and has a diameter between 70 and 120 nanometer…… it is a round virus, in some cases pleomorphic, with a diameter between 70 and 120 nanometers, containing single helix NRA. The virions are coated in a covering from which long clavate projections radiate, 20 nanometers long, found in all members of the group.
From an antigenic point of view cross reactions have been found between human coronavirus and that in mice.
Cultivation: Human coronaviruses are cultivated in human diploid cells in which they determine a cytopathogenic effect. Some strains have been adapted in monkey kidney cells.
Experimental infection: some stipites of human origin are pathogens for newborn mice in which they determine, after intracerebral inoculation, acute mortal encephalitis.
Haemagglutination power: Human coronaviruses agglutinate human and monkey erythrocytes at 4°C: rat and mouse erythrocytes at room temperature or 37°C.

The students on the degree course in medicine and surgery, who did not know the subject, failed the exam (just as most of the countless so-called experts should be failed, who speak, advertise themselves and decide, offending the fundamental bases of virology and medicine in general).


THIS EXPERTS HAVE TRIGGERED A SPIRAL OF ESCALATION, WHICH NOBODY SEEMS TO WANT TO STOP.


Die Medizienstudenten, die ueber dieses Argument nicht Bescheid wussten, fielen durch die Pruefung durch, (sowie ein Grossteil der unzaehligen sogenannten Experten, die Vortraege halten, sich in den Vordergrund draengen, die Entscheidungen treffen, wobei sie die Grundfeste der Virologie und der Medizin mit Fuessen treten.)


DIESE EXPERTEN HABEN EINE SPIRALE DER ESKALATION IN GANG GESETZT, DER KEINER MEHR EINHALT GEBIETEN WILL.


I studenti del corso di laurea di medicina e chirurgia, che non sapevano l’argomento, venivano rimandati (come saranno da rimandare gran parte dei innumerevoli cosiddetti esperti, che parlano, si pubblicizzano e decidono, offendendo le basi fondamentali della virologia e della medicina in generale).


QUESTI ESPERTI HANNO INNESCATO UNA SPIRALE, CHE NESSUNO SEMBRA VOLER FERMARE


„UND ICH HABE AUF SOZIALE DISTANZIERUNG UND MASKENTRAGEN VERTRAUT“

Es wird immer deutlicher, dass die Aerosoluebertragung den Hauptweg fuer das Coronavirus darstellt. Massnahmen, die die Uebertragung ueber Aerosol verringern koennten, wurden bisher nicht ergriffen, sondern es wurden verschiedene Fehler begangen, die die Lage taeglich weltweit weiter verschlechtern:

Fehler 1: Gesichtsmaskenempfehlung fuer Coronakranke:

Sie verschlechtert durch die erhoehte endogene Viruslast aufgrund der reduzierten Lungenclearance und der erhoehte Lungenaktivitaet (um das circa 30 fache) die Krankheit mit haeufig letalem Ausgang.

Fehler 2: Gesichtsmaskenpflicht fuer noch nicht Infizierte (es sei denn, sie kommen mit Kranken in Kontakt wie Aerzte, Pflegepersonal).

Sollte eine gesunde Person, Maskentraeger, mit dem Coronavirus in Kontakt kommen (vor dem nur die Masken FFP2, FFP3 schuetzen), wird er wahrscheinlich einen schweren Krankheitsverlauf aufweisen. Dies aufgrund der erhoehten endogenen Viruslast infolge der verringerten Lungenclearance. Unser Organismus verfuegt prinzipiell ueber vier Ausscheidungswege: Niere, Darm, Haut und Lunge. Wird einer dieser Wege eingeschraenkt, fuehrt dies zu zum Teil toedlichen Krankheitsverlaeufen.

Fehler 3: Anordnung sozialer Distanzierung ohne jeglichem Unterschied zwischen jung und alt.

Gerade die jungen Menschen, die den Virus unter sich verbreiten ohne zu erkranken, bilden somit ein immunologisches Schutzschild um die Schwaecheren. Sie werden allerdings von offiziellen Stellen durch soziale Distanzierung von dem Aufbau der natuerlichen Herdenimmunitaet abgehalten. Diese soll dann sobald als moeglich mit einer gefaehrlichen Impfung erzeugt werden.

Fehler 4: Zurueckstellung aller notwendigen Korrekturen mit Hinweis auf die Impfung.

                Die Impfung ist aus zweierlei Gruenden sehr gefaehrlich:

  1. die Forschung nach dem Impfstoff ist mittlerweile zu einem kommerziellen Wettlauf in Billionenhoehe auf verschiedenster Ebene geworden. Notwendige Entwicklungszeiten, neutrale Ethikkommissionen, objektive Berichterstattung der Medien, unabhaengige Expertenmeinungen und eine dem Gemeinwohl verpflichtete Politik sind diesem Wettlauf zum Opfer gefallen, und schlimmer noch: die Sicherheit des Impfstoffes.
  2. Zum ersten Mal in der Geschichte wird eine Massenimpfung waehrend einer Epidemie (und hier sogar waehrend einer Pandemie) durchgefuehrt werden. Dies trotz den allgemein bekannten schweren Komplikationen einer Impfung bei Personen, die sich eventuell in der Inkubationszeit befinden. Besonders besorgniserregend ist, dass all dies grossteils an Personen durchgefuehrt wird, fuer die das Coronavirus keine bedeutende Gefahr darstellt.

Eine Impfung von Kindern ist ein Verbrechen an die Menscheit.

Fehler 5: Fehldeutung des Uebertragungweges des Virus.

Dieser erfolgt (ueber Aerosol) fast ausschliesslich in geschlossenen, schlecht geluefteten Raeumen. Es wurden gegen bessern Wissens in keinster Weise wirksame Massnahmen ergriffen, die hauptsaechlich in der Verbesserung des Raumklimas in allen Bereichen haetten bestehen muessen.

Dies ist die Aufgabe, die sich jetzt stellt.

ERRARE HUMANUM EST, PERSEVEREARE AUTEM DIABOLICUM

Weiterhin ist es unabdingbar, keine weiteren Nebenschauplaetze als Ablenkmanoever zu eroeffnen wie: woechentliche Reihenuntersuchungen an Schulen, Coronatagebuch, geziehlte Eindaemmung von SARS-CoV-Clustern oder duestere Vorhersagen einer zweiten, gefaehrlichen Welle.Die Wahrheit ist wie ein Loewe. Man muss sie nicht verteidigen. Lass sie einfach los. Sie wird sich selbst verteidigen.


“AND I TRUSTED DISTANCING AND MASKS”

It is becoming increasingly evident that the main means of transmission of the Coronavirus is by aerosols. Measures that should have reduced this transmission have not yet been taken, whereas several serious errors have been made, which have led to a progressive deterioration of the situation day for day worldwide.

Error 1: Advice/obligation for people with Coronavirus to wear masks:

                Due to reduced pulmonary clearance, masks increase the endogenous viral load. This, combined with the increased pulmonary activity induced by the masks (about 30 times higher), causes an aggravation of the disease with frequent fatal outcome.

Error 2: Obligation to wear masks for people not yet infected (except people in contact with the sick like doctors, nurses etc., where the only protective mask against the virus, the FFP2,3, is necessary)

                A healthy person, wearing a mask (except FFP2,3 worn in an absolutely airtight manner, which is extremely rare) who comes into contact with an infectious person, catches the virus anyway- But their situation will get worse because of the increased endogenous viral load as a result of the reduced pulmonary clearance (caused by the mask). Another reason why there is a high mortality in the countries currently affected, where nearly everyone wears masks. N.B. our organism has four main pathways for the elimination of toxins: kidneys, intestine, skin and lungs. The reduction of one of these pathways results in a serious impairment of health, which can be fatal.

Error 3: Obligatory social distancing regardless of age.

                                Young people especially spread the virus among themselves without getting ill and create a protective immunological shield around the weaker: the elderly and the sick. Government rules prevent them from forming a natural herd immunity, which will then be created as soon as possible by a vaccination dangerous for everyone.

Error 4: Postponing all the necessary measures to be taken in the “hope” for a vaccine:

                Vaccination is dangerous for two reasons:

  1. The search for a vaccine has now degenerated into a commercial/political race in the order of billions of euro at very different levels. That is why the necessary time to develop a safe vaccine, neutral ethical committees, objective information from the media, opinions of independent experts, responsible public health policies, and worse still: the safety of the vaccine have all been sacrificed.
  2. For the first time in the history of medicine mass vaccination is being programmed during an epidemic (and specifically during a pandemic). This despite the well known, even extremely serious complications of vaccinating people in the incubation period. Even more alarming is the fact that the vaccination will mainly be carried out on people for whom the coronavirus is not significantly clinically dangerous. To perform it even on children is a crime against humanity.

Error 5: Mistaken identification of the means of transmission of the virus:

                The virus is almost exclusively transmitted by aerosols in closed, badly ventilated environments. In this respect, in no way have efficient measures been taken to deal with the emergency. These should have led mainly to an improvement of the microclimate in indoor environments.

ERRARE HUMANUM EST, PERSEVERARE AUTEM DIABOLICUM

Furthermore it is imperative to avoid opening additional secondary fronts, intended solely as diversion tactics (broad spectrum swabs, travel limitations, alarmism for schools, Sars CoV-Clusters and distressing forecasts of a second wave.

The truth is like a lion: you don’t have to defend it. Let it loose, it will defend itself.


„E MI SONO FIDATO DEL DISTANZIAMENTO E DELLE MASCHERINE”

Diventa sempre più evidente, che la via principale di trasmissione del Coronavirus è rappresentata dall’aerosol. Misure, che avrebbero dovuto ridurre tale trasmissione, non sono state fin’ ora intraprese, invece sono stati commessi diversi errori anche gravi, responsabili di un progressivo peggioramento della situazione giorno per giorno in tutto il mondo.

Errore 1: Consiglio/obbligo per malati di Coronavirus di indossare mascherine:

                Le mascherine aumentano, a causa della ridotta clearance polmonare, la carica virale endogena. Questo comporta, associata alla aumentata attività polmonare indotta dalle mascherine (circa 30 volte superiore) un aggravamento della malattia con frequente esito letale.

Errore 2: Obbligo di indossare mascherine per persone ancora non infette (eccetto persone a contatto con malati quali medici, infermieri ecc., dove è necessario quale unica mascherina protettiva contro il virus la FFP2,3)

                Una persona sana, portatore di mascherina (eccetto FFP2,3 indossato in maniera assolutamente stagna, il che è rarissimo) che viene a contatto con una persona infettante, contrae il virus lo stesso. Ma la sua situazione peggiorerà a causa della aumentata carica virale endogena in seguito della ridotta clearance polmonare (sempre dovuta alla mascherina). Anche per questo si assiste ad una mortalità elevata nei paesi attualmente colpiti, dove quasi tutti sono portatori di mascherine. Nota bene: il nostro organismo dispone di quattro principali vie di eliminazione di tossine: reni, intestino, cute e polmone. La riduzione di una di queste vie comporta una grave compromissione della salute, anche mortale.

Errore 3: Obbligo di distanziamento sociale senza alcuna differenza tra giovani ed anziani.

                Proprio i giovani, che diffondono tra di loro il virus senza ammalarsi, creano uno scudo protettivo immunologico attorno ai più deboli: anziani, ammalati. Disposizioni statali impediscono loro di creare la naturale immunità di gregge, che poi sarà istituita il più presto possibile da una vaccinazione pericolosa per tutti.

Errore 4: Rimandare tutte le misure necessarie da intraprendere nella “speranza” del vaccino:

                La vaccinazione è pericolosa per due motivi:

  1. La ricerca del vaccino ormai e degenerata ad una corsa commerciale/politica nell’ordine di billioni di euro a diversissimi livelli. E per questo i tempi necessari per lo sviluppo di un vaccino sicuro, comitati etici neutri, informazione oggettiva da parte delle media, pareri di esperti indipendenti, la politica responsabile della salute pubblica, e ancora peggio: la sicurezza del vaccino sono stati sacrificati.
  2. Per la prima volta nelle storio della medicina viene programmata una vaccinazione di massa durante una epidemia (e nel caso specifico durante una pandemia). Questo nonostante delle ben note, anche gravissime complicazioni di una vaccinazione di persone, che si trovano nel periodo di incubazione. Ancora più preoccupa è il fatto, che la vaccinazione sarà eseguito maggiormente in persone, per le quali il coronavirus non costituisce un pericolo clinicamente significativo. Effettuarla addirittura in bambini costituisce un crimine all’umanità.

Errore 5: Sbaglio nella individuazione della via di trasmissione del virus:

Il virus si trasmette quasi esclusivamente tramite aerosol in ambienti chiusi, mal aerati. In tale ottica non sono state intraprese in alcun modo delle misure efficaci per affrontare l’emergenza, che dovevano portare principalmente al miglioramento del microclima in ambienti chiusi, E CHE TUTT’ORA NON VENGONO INTRAPRESE.

ERRARE HUMANUM EST, PERSEVERARE AUTEM DIABOLICUM

Inoltre è indispensabile di evitare di aprire ulteriori fronti secondari, che mirano esclusivamente quale manovre di depistaggio (tamponi a largo spettro, limitazioni di viaggi, alarmismo per le scuole, Sars CoV-Clusters e previsioni angoscianti di una seconda onda).

LA VERITA’ E’ COME UN LEONE. NON AVRAI BISOGNO DI DIFENDERLA. LASCIALA LIBERA. SI DIFENDERA’ DA SOLA.

Read the article in English :

Lesen Sie den Artikel auf Deutsch :


Die Wahrheit ist wie ein Löwe. Man muss sie nicht verteidigen. Lass sie einfach los. Sie wird sich selbst verteidigen, oder: DER FALSCHE WEG: ANALYSE DER ANTI-CORONA MASSNAHMEN UND DER URSACHEN FUER IHR VERSAGEN

Abstrakt

Das Coronavirus, ein schon seit einem halben Jahrhundert wohlbekanntes Virus, vergleichbar mit dem Influenzavirus, hat den Grossteil der Regierungen in einen Alarmzustand versetzt. Da sie als Schmier und Troepfcheninfektion angesehen wurde, wurden verschiedene Massnamen ergriffen, die sich allerdings nicht nur als unwirksam sondern sogar als schaedlich herausgestellt haben. Somit wurde der Weg fuer die Impfung geebnet, ueberfluessig und potentiell gefaehrlich wie alle neu entwickelten Impfstoffe. Auf den einzigen Uebertragungsweg des Virus, der ausschliesslich ueber Aerosol erfolgt, wird nicht eingegangen, wodurch sich die globale Situation Tag fuer Tag verschlechtert.

Der Anfang der Virologie geht auf 1780 vor Christus zurueck (Codex Eschnunna)(1), als ein Fall von Tollwut beschrieben wurde. Cornelius Aulus Celsus (2) gab ihm im ersten Jahrhundert vor Christus den Namen „Virus“, 1882 forderten Adolf Mayer (3)und 1898 Martinus Willem Beijerinck (4) die Existenz eines nicht filtrierbaren Erregers. Ihre Theorie wurde mit der Erfindung der Elektronenmikroskopes 1931 bestaetigt und somit waren die Grundlagen fuer die Virologie als Wissenschaft geschaffen.

Diese Wissenschaft wurde mit dem Coronavirus, einem seit mehr als 50 Jahren bekannten Virus (5) konfrontiert, der eine Pandemie verursacht hat, die in die lange Liste der Epidemien und Pandemien der juengeren Zeit einzureihen ist. Der Umgang mit dieser Epidemie wurde jedoch sofort sehr widerspruechlich in der virologischen Gemeinschaft diskutiert, was fuer eine Wissenschaft unueblich ist (1+1=2, nicht 3 oder 4).

Die verschiedenen Regierungen, von der Epidemie in Alarm versetzt, haben mehr oder weniger dieselben praeventiven Massnahmen getroffen wie Schutzmasken, Mobilitaetseinschraenkungen, soziale Distanzierung, und Identifikation und Isolierung von viruspositiven Personen.

Analyse der praedisponierenden demographischen und geographischen Faktoren:

Bevor hier die Auswirkungen der vorbeugenden Massnahmen auf den Verlauf auf die Epidemie untersucht werden, wird auf zwei grundlegende und praedisponierenden Faktoren fuer den Verlauf der Mortalitaetskurven eingegangen, und dies anhand Italiens, stellvertretend fuer den Grossteil der europaeischen Laender.

  1. Demographischer Aspekt:

Die Anzahl der ueber 90 jaehrigen ist von 2010 bis 2017 von ungefaehr 400.000 auf mehr als 700.000 angestiegen.

2018 waren in Italien mehr als 2.2 Millionen Buerger ueber 85 Jahre registriert (Primat fuer Europa). Davon leben zur zeit insgesamt mehr als 300.000 in Altersheimen. Dies entspricht der Stadt Venedig, voll mit seinen taeglich 60.000 Touristen und die Gondolieren eingeschlossen.

Italien bei tag
Italien bei nacht
Italien bei der Coronaepidemie


91% der Exzessmortalitaet verteilt sich auf den Norden mit einem Anstieg von 52%, in den anderen Gebieten geht man von einem Anstieg von 1.1 % aus. Auf Sizilien ergab sich sogar eine Verringerung der Mortalitaet von ungefaehr 5%. Die am meisten betroffenen Regionen befinden sich also im Norden, mit seinem hohen Industrieanteil mit all seinen spezifischen umweltbedigten, klimatischen und arbeitsmaesigen Faktoren.

Analyse der Vorbeugemassnahmen

                Ein eventueller Einfluss der Gesichtsmasken auf die Uebertragung von respiratorischen viralen Krankheiten ist bisher wissenschaftlich nicht unterstuetzt (7). Weiterhin beruecksichtigen die Empfehlungen/Verpflichtungen, diese zu tragen in keinster Weise die Einschraenkungen, denen sie als Arbeitsgeraete (8) unterworfen sind hinsichtlich der Tragedauer, der Benutzung von Personen mit Herz-Lungenproblemen, bei Kindern und Schwangeren. Die fehlenden Informationen bezueglich dieser Risiken gedeuteten eine Gefaehrdung des Allgemeinwohles (9)mit zum Teil schweren, auch bleibenden Schaeden der Gesundheit. Aber trotzdem wird weiterhin auf der ganzen Welt deren Benutzung empfohlen/vorgeschrieben, vielleicht nur um die Bevoelkerung zu beruhigen.

Auch hinsichtlich der sozialen Distanzierung als Mittel zur Verringerung der Ansteckung bei respiratorischen Viruserkrankungen (Influanzaviren und aehnlichen wie das Coronavirus) gibt es bisher in der medizinischen Literatur keinen Nachweis. Trotz alledem wurden diese Massnahmen auf fast das ganze Umfeld sowohl im Freien (auch am Strand, am Meer, bei oeffentliche Festen aller Art) als auch in geschlossenen Raeumen ausgedehnt.

Analyse der Effizienz der angetroffenen Massnahmen

Es sind keine signifikanten Unterschiede hinsichtlich des Verlaufes der Mortalitaet nach Beginn selbiger Massnahmen festzustellen. Die Sterblichkeitskurven dieses Jahres aufgrund des Coronavirus ist im Verlauf sehr aehnlich mit der Sterblichkeitskurve aufgrund des Influenzavirus im Jahre 2016/17

www.salute.gov.it/portale/covid/SISMG_sintesi_ULTIMO.pdf del 15/6/2020 (10)

Sie sind vergleichbar mit zwei Gauss’sche Kurven mit identischen Parametern bis auf ihr Maximum. Zieht man jedoch die verminderte Sterblichkeit in den vier vorhergegangenen Monaten davon ab, so ergeben sich keine bedeutenden Unterschiede.

Analyse der Gruende fuer das Fehlschlagen der getroffenen Massnahmen

Die Gruende fuer die Erfolglosigkeit der angetroffenen Massnahmen liegen in der falschen Auffassung des Uebertragungsweges des Coronavirus. Die Verbreitung des Coronavirus, wie auch die des Influenzavirus, erfolgt nicht ueber Schmier und Troepfchenuebertragung (der falsche Weg), sondern ausschliesslich ueber Aerosol, wie bereits ab 21/4/2020 der wissenschaftlichen, vor allem virologischen Gemeinschaften, und staatlichen Stellen vorgestellt worden sind (Wegener, der Weltbildzertruemmerer (11) und: Das Aerosol als einzig relevanter Uebertragungsweg des Coronavirus: epidemiologische Analyse (12). Diese Auffassung ist seit ein paar Tagen auch von der WHO geteilt worden. Das Virus verhaelt sich in der Luft wie die Schwebeteilchen des Rauches, dessen Teilchen vergleichbare Dimensionen (13) haben.

Diese Theorie wird weiterhin von Beobachtungen in Deutschland bekraeftigt, wo es zu einer hohen Infektionsrate von Personen in geschlossenen Raeumen Berichten (Chorgemeinschaft, Grosschlachterei).

Die dazu benoetigte hohe Viruslast, in Form von Aerosol, wurde durch die Anwesenheit von asymptomatischen Ausscheidern im Zusammenhang mit weiteren Faktoren verursacht, wie erhoehte Ausscheidung durch erhoehte Atemtaetigkeit (Chor), niedrige Arbeitstemperatur (Schlachterei) und ungenuegende Lueftung, um eine akustische (Chor) oder energetische (Schlachterei) Dispersion zu minimieren.

Betrachtungen hinsichtlich der natuerlichen Abwehr gegen das Coronavirus

Die fuer die Gesundheit gefaehrliche Uebertragung des Coronavirus erfolgt in geschlossenen Raeumlichkeiten (Altersheime, oeffentliche Gebaeude und Verkehrsmittel, Krankenhaeuser, Arbeitsstaetten), wo die erhoehte Visuslast aufgrund der unzureichenden Lueftung (14) haeufig zu einem zum Teil schweren Krankheitsverlauf fuehrt, vor allem bei Personen mit bestehenden Vorerkrankungen. Wie vielmals aufgezeigt, ist die Qualitaet der Innenraumluft eng an das Uebertragungsrisiko von respiratorischen viralen Erkrankungen gekoppelt (15).

In entsprechend geluefteten Innenraeumen erfolgt die Infektion nur mittels einer geringen Viruslast, die, vergleichbar mit einer aktiven Impfung, die eine immunologische Antwort ohne Krankheitszeichen hervorruft.

Entwicklungsgeschichtlich her gesehen, wurde ein Fremder, ein Aussenstehender als potenziell gefaehrlich fuer die Gemeinschaft betrachtet und ausgegrenzt: soziale Distanzierung. Innerhalb der Gemeinschaft wurde allerding das Gegenteil praktiziert: soziale Naehe. Diese erfolgte, um eine Uebertragung der Viren ueber Aerosol auch im Freihen zu ermoeglichen, um so die Herdenimmunitaet zu erzeugen. Im Norden Europas reicht es hierfuer, sich auf weniger als einen Meter anzunaehern (Haendegeben), in den waermeren Gebieten des Sueden Europas ist das Aerosol aufgrund der hoeheren Temperatur instabiler, weswegen ein geringerer Abstand dazu notwendig ist (Kuesschen auf di Wange). In den Polargebieten, wo eine Uebertragung ueber Aerosol aufgrund der dortigen Temperaturen unmoeglich ist, wird die noetige Naehe mit gegenseitigem Nasenreiben garantiert.

Wenn die Menschheit in ihrer Evolution die zur zeit von den Regierungen angeordneten Massnahmen angewendet haette, wuerde sie bereits seit Langem zu den ausgestorbenen Arten zaehlen.

Deswegen muss der Replikationsfaktor (dieser gibt die durchschnittliche Anzahl der Leute an, die ein Infizierter ansteckt bevor er wieder gesundet oder stirbt) in der gesunden Bevoelkerung hoch sein. Natuerlich muessen aeltere und kranke Menschen geschuetzt werden, wie es aber seit jeher ueblich ist. Somit wird das immunologische Gedaechtniss der Gemeinschaft garantiert ist, unerlaesslich fuer das Ueberleben des Homo sapiens

Die Suche nach Infizierten mittels Corona Warn Apps oder Corona Reihenuntersuchungen (mit erheblichen Kosten verbunden), um sie dann unter behoerdlich angeordnete Quarantaene zu stellen, greift schwerwiegend in die Abwehr des Menschen gegen diese Infektionskrankheit ein. So wird kuenstlich die Notwendigkeit einer Reihenimpfung erzeugt, die nicht nur mit weiteren erheblichen Kosten verbunden.

Es ist zu befuerchten, dass der jaehriche Anstieg der Mortalitaet Ende des Sommers dem Coronavirus zugeteilt wird (wie bereits von vielen oeffentlichen Stellen seit Monaten angekuendigt), um somit die nationale Notwendigkeit einer Massenimpfung zu schaffen.

Betrachtungen hinsichtlich der Impfung

Laut WHO gibt es zur zeit mehr als140 Forschungszentren hinsichtlich des Coronavirusimpstoffes, alle im abgekuerztem Verfahren (Notfallklausel) aufgrund der “aktuellen“ Notwendigkeit, mit all den damit verbundenen Gefahren fuer alle an der Forschung Beteiligten wie die freiwilligen Probanden, die Laborangestellten, die Mediziener (siehe den beinahe Supergau im Bereich der Herstellung von Impfstoffen 1967 in Marburg, Deutschland (16)). Ausserdem sind fuer die zweite Phase als Freiwillige auch Kinder vorgesehen, im klaren Widerspruch zu den Direktiven der UE (17), die eindeutig festlegen, dass: „dieses Objektiv nur ueber eine gruendliche Untersuchung erfolgen kann, die eine deutliche klinische Relevanz fuer Kinder nachweist“. Diese Relevanz fuer Kinder liegt jedoch nicht vor, da Kinder nicht vom Coronavirus betroffen werden (18), wie vom Grossteil der Weltliteratur berichtet wird.

Hinsichtlich der Risiken fuer alle an der Forschung beteilgten Personon, waere es eventuell sicherer gewesen, die Forschung auf wenige anerkannte Zentren auf der Welt zu beschraenken, autorisiert von Ethikkommission die „unabhaengig von Sponsor, Geldgebern, Forschern und von unzulaessigen auesseren Einfluessen jeglicher Art sei es politischer, beruflicher, wirtschaftlicher oder institutioneller Natur“ sind, wie von der Europaeischen Patientenakademie (19) gefordert.

Der Impfstoff, der letztendlich aus diesen vielzahligen Forschungsreihen, unter Missachtung der normalerweise vorgeschriebenen Testdauer, gewonnen werden wird, setzt die Bevoelkerung einem nicht kalkulierbarem Impfrisiko aus mit eventuellen schwersten Schaedigungn fuer die Gesundheit.

Jeder Mediziner, der den Eid des Hippokrates geschworen hat, muss sich wenigstens der Impfpflicht fuer Kinder widersetzen, die keinerlei Nutzen aber nur eventuelle Schaeden daraus ziehen.

Schlussfolgerungen

Wenn man nicht umgehend auf den einzigen Uebertragungsweg des Coronavirus (der ueber Aerosol) einwirkt, setzt man weiterhin die Bevoelkeurung einem hohen Gesundheitsrisiko aus. Die vorzunehmenden Massnahmen sind nicht Schutzmasken oder soziale Distanzierung, sondern eine angebrachte Lueftung der Gebaeude.

Sollten dahingehende Massnahmen nicht unverzueglich eingeleitet werden, wird eine weitere Pandemie aufgrund eines anderen Virus wiederum die Politik alarmieren mit all den Folgen dieses Jahr.

Die Geschichte der Medizin ist von grossen Persoenlichkeiten gepraegt worden, die nie den Kontakt mit Kranken gescheut haben wie Mutter Teresa von Kalkutta, Pasteur, Koch, Virchow , und von bedeutenden Wegbereitern in der Geschichte der Virologie. Wir muessen uns wehren, dass ihr Gedaechtniss und ihr Einsatz zu Nichte gemacht wird, indem wir die Medizin auf falsche Grundfeste bauen. Dies wird am Ende die Schwaechsten von uns treffen, unsere Kinder (20).

Bibliographie

  1. https://www.google.com/search?q=codex+eschunna&oq=codex+eschunna&aqs=chrome..69i57j0l2.8426j0j4&sourceid=chrome&ie=UTF-8
  1. www.salute.gov.it/portale/covid/SISMG_sintesi_ULTIMO.pdf del 15/6/2020
  1. https://www.vasodipandora.net/2020/05/29/der-weltbildzertruemmerer-wegener-und-das-coronavirus/
  1. https://www.vasodipandora.net/2020/05/29/aerosol-als-der-einzig-relevanter-uebertragungsweg-des-coronavirus-epidemiologische-analyse/
  1. https://link.springer.com/chapter/10.1007/978-3-642-29942-1_16
  1. https://www.vasodipandora.net/2020/07/26/luft-ist-leben/
  1. https://pubmed.ncbi.nlm.nih.gov/12950586/   Rudnick and Milton
  1. https://www.tagesspiegel.de/gesellschaft/erster-ausbruch-des-marburg-virus-was-vor-50-jahren-in-den-behringwerken-geschah/20176074.html
  1. https://eur-lex.europa.eu/legal-content/IT/LSU/?uri=CELEX:32001L0020
  1. https://www.vasodipandora.net/2020/05/29/modell-zur-erklaerung-der-geringen-infektionsrate-bei-kindern-durch-das-coronavirus-epidemiologische-anatomische-und-physiologische-analyse/
  1. https://www.google.com/search?q=Comitato+etico+(CE)+-+EUPATI&oq=Comitato+etico+(CE)+-+EUPATI&aqs=chrome..69i57j33l3.6976j0j4&sourceid=chrome&ie=UTF-8

Damit verbundene Veroeffentlichungen

Wegener der Weltbildzertruemmerer

Aerosol als einzig relevanter Uebertragungsweg des Coronavirus – epidemiologische Analyse

Modell zur Erklaerung der geringen Infektionsrate bei Kindern durch das Coronavirus: epidemiologische, anatomische und physiologische Analyse

Protektive Wirkung des Rauchens gegen Infektion duch das Coronavirus

Coronavirus und Masken

Luft ist Leben

Kinder und das Coronavirus


The truth is like a lion: you don’t have to defend it. Let it loose; it will defend itself, or: THE WRONG PATH: ANALYSIS OF THE ANTI CORONAVIRUS MEASURES AND THE REASON OF THEIR FAILURE

Abstract:

The Coronavirus, well known for more than half a century and similar to the Influenza virus, has alarmed most governments. Believing the mode of transmission to be through contact and droplets, the measures taken to deal with the emergency have proved not only inefficient but downright harmful. Thus the way has been cleared for vaccination, superfluous and potentially dangerous like all innovative vaccinations. No action is taken on the true mode of transmission of the virus, which occurs exclusively through aerosols, aggravating the global situation day by day.

Virology originated in 1780 BC (Codex Eschnunna) (1), where a case of rabies was described. In the first century BC Cornelius Aulus Celsus (2) defined the agent of this disease a virus, in 1882 Adolf Mayer (3) and in 1898 Martinus Willem Beijerinck (4) indicated the existence of an infective agent non-filterable and indemonstrable with the methods at their disposal. The advent of the electronic microscope in 1931 confirmed their theory and virology became a science.

This science has been confronted with the coronavirus, a respiratory virus already known for more than half a century (5) and already then studied in detail, which has generated a pandemic to include in a long list of epidemics and pandemics in recent times. The approach to this event however has been immediately discussed in the virological world in a very contrasting way, unusual for an established science (1+1=2 and not 3 or 4).

The various European governments, alarmed by the course of the epidemic, have more or less adopted the same transmission preventive measures such as: protective devices (masks and gloves), restrictions on movement, distancing even in the open, identification and isolation of healthy carriers.

ANALYSIS OF THE PREDISPOSING DEMOGRAPHIC AND GEOGRAPHICAL FACTORS

Before analyzing the efficacy of these protective measures on the epidemic, we need to consider other fundamental predisposing factors which affect the progress of the curves (Italy is considered to be representative for most European countries) for the following aspects:

1) Italian demographic aspect

Since 2010 the number of over 90s has risen from about 400 thousand to about 700 thousand in 2017.

In 2018 those recorded aged over 85 were 2.2 million (highest figure in Europe according to ISTAT). This means a continuous increase in the number of elderly people in care homes. At present there are more than 300 thousand elderly residents in facilities in Italy. A number which corresponds to the city of Venice with its 260 thousand inhabitants, its 60 thousand odd tourists and its gondoliers included.

Italy daylight
Italy night vision
Italy by Coronavirus


91% of the excess mortality occurred in the North with an increase of 52%, in the rest of the country it goes from an average increase in mortality of 1.1% down to an actual 5% reduction in mortality in Sicily. The more industrialized Northern areas were hit, with their specific environmental, climatic and working factors.

ANALYSIS OF THE PREVENTIVE MEASURES

A significant role of masks in relation to the transmission of viral infectious diseases has never been proved scientifically (7). Furthermore the advice/obligation to wear them does not take into account the regulations in force regarding their use (being work equipment(8)) as regards the time of use and their use by people with cardio-respiratory pathologies, pregnants and children. The lack of information on the risks incurred by their use, implies a serious risk to public health with even irreversible long term damage (9). But the use of masks is advised throughout the world, may be only to reassure the public.

Neither does distancing to reduce transmission of the virus in the population find any evidence in the medical literature regarding a possible reduction in mortality related to flu-like respiratory diseases and similar. Nevertheless, this measure is still in force in virtually any living environment both in the open (even on the beach, at the sea, at the stadium, public patron saints’ festivals etc.), and in indoor environments.

ANALYSIS OF THE EFFICACY OF THE MEASURES

In fact, there have been no significant variations in the course of mortality after the implementation of these measures. The mortality curve of the Influenza virus in 2016/17 and that of the Coronavirus, in 2019/2020(both respiratory viruses, similar to each other) have a statistically overlapping pattern.

www.salute.gov.it/portale/covid/SISMG_sintesi.pdf del 15/06/2020 (10).

These represent two Gauss curves with identical slope parameters except for the height of the curves. Detracting the reduced mortality in the 4 months preceding the Coronavirus epidemic from the peak of the curve, there are no significant differences.

The reason for the failure of the measures undertaken, responsible for the constant increase in deaths, is determined by the insistence on the mistaken mode of transmission, (see title), previously considered through droplets or contact. The mode of transmission of the coronavirus is instead exclusively through aerosols, as already stated on 21/4/2020 to the scientific community (General observations on the Coronavirus (11), Aerosol as the only significant mode of transmission of Coronavirus (12)) and then also to various government and non-government bodies, finally in part accepted by the World Health Organization.

The behavior in the aerosols is comparable to passive smoking , whose particles, as regards dimensions, are superimposable (13).

This evidence is further reinforced by observations in Germany, where many people in indoor environments have been infected (choir group, more than 1500 workers in a slaughterhouse). The high viral load, present in the form of aerosols, was due to the presence of asymptomatic people in the infectious phase and to the coexistence of other factors, including the conspicuous emission of the virus through increased respiratory activity (choir), the greater presence of the virus in the environment due to the low working temperature (slaughterhouse) and insufficient ventilation to reduce the sound dispersion (choir) and energy leakage (slaughterhouse).

CONSIDERATIONS ON THE NATURAL REPLY TO CORONAVIRUS

The dangerous transmission for health occurs in closed spaces (care homes, workplaces, offices, underground, conference halls etc), where the high viral load caused by insufficient ventilation (14) often leads to a serious evolution, especially in those with preexisting pathologies. As extensively demonstrated, the air quality in such environments is closely related to the risk of contracting infectious respiratory diseases (15) and in this specific case coronavirus.

In open spaces, but also in well ventilated indoor environments, this transmission occurs only with a very low viral load, similar to an active vaccine, which induces an immunological response with no evident signs of illness.

Anthropologically in closed communities the outsider was excluded, considered dangerous, while inside the community anti-distancing measures were applied to guarantee a passage of infective agents transmitted by aerosols (virus) even in the open. In Northern Europe it was sufficient to get less than a meter close for this mode of transmission, i.e. a handshake distance. In warmer countries aerosols are more volatile in the air, so a more intimate approach is necessary (a kiss on the cheek). In the Polar zones, transmission at a distance being impossible, it was ensured exclusively by rubbing noses.

If humankind had applied the laws laid down at present by most governments, it would have long been extinct

Therefore the replication factor, which indicates how many people are infected by an infected person, must be high in the healthy population (obviously the elderly or those with concomitant pathologies are shielded, as has always happened), thus guaranteeing the immunological memory essential for the survival of the species.

The identification of positives with apps like immune or through mass testing (at considerable cost to the community) and their isolation, seriously intervenes on the natural course of human defense against infectious diseases. Thus artificially creating the need for a vaccine again at considerable extra cost to the community.

There is a danger that the increase in mortality at the end of the summer, which happens every year like the winter peak during the flu epidemics, will be attributed to the Coronavirus (as already announced for months) and confirm the immediate national need for the vaccine.

CONSIDERATIONS ON VACCINATION

At present vaccine trials around the world, according to the WHO, are over 140 with multiple testing on people, all fast-tracked because of the emergency, with inherent dangers for the volunteers but also for the people employed in the research (see the terrifying experience in 1967 for the Marburg virus (16)). Moreover in phase 2 child volunteers are planned, in stark contrast to EU directives (17), which state “this objective can only be achieved through in-depth trials on drugs which may have significant clinical value for children”. This clinical value for children does not exist, because they are not affected by coronavirus, as demonstrated by most of the literature (18).

Considering the risks inherent in the trials, maybe it would have been wiser to limit these trials to a few centers around the world, authorized by ethics committees, which are, as postulated by the European Patients’ Academy (19): independent of sponsors, financiers, experimenters and undue influence (e.g. politicial, istitutional, professional or commercial).

The vaccine eventually obtained from these multiple trials, which do not respect the time normally considered necessary to guarantee a safe vaccine, puts those to be subjected to vaccination at serious risk, with at present unquantifiable but potentially very serious harm. Any doctor must remember the Hippocratic oath and must at least oppose the vaccination requirement for children, for whom there is no benefit from this treatment, only high risks.

CONCLUSIONS

With no intervention on the only mode of transmission of the virus (aerosols), populations continue to be exposed to a serious health risk. The precautions to be taken are neither masks (harmful) nor distancing (counterproductive), but adequate ventilation in buildings.

If these necessary preventive measures are not taken, a subsequent pandemic caused by another virus will alarm the political world again with all the consequences already experienced this year.

The history of medicine is steeped in great figures, who never feared contact with the sick, like Mother Teresa of Calcutta, Pasteur, Koch, Virchow, and great protagonists of the history of virology. Let’s not destroy their memory and their commitment, establishing medicine on false assumptions, which in the end will affect the weakest, our children (20).

BIBLIOGRAPHY

  1. https://www.google.com/search?q=codex+eschunna&oq=codex+eschunna&aqs=chrome..69i57j0l2.8426j0j4&sourceid=chrome&ie=UTF-8
  2. https://www.cambridge.org/core/journals/classical-review/article/celsus-de-medicina-aulus-cornelius-celsus-ueber-die-artzneiwissenschaft-ubersetzt-und-erklart-von-eduard-scheller-zweite-auflage-von-walther-frieboes-braunschweig-vieweg-und-sohn-1906-8vo-pp-xlii-862-tafeln-iv-m-18/083432E6C5C31FB9539507FA69583E42
  3. https://www.buecher.de/shop/fachbuecher/adolf-mayer-agronom/broschiertes-buch/products_products/detail/prod_id/31684669/
  4. https://www.britannica.com/biography/Martinus-W-Beijerinck
  5. https://www.vasodipandora.net/2020/05/30/virus-da-poco-conosciuto-e-ben-conosciuto-decenni/
  6. https://www.udinetoday.it/attualita/indagine-inps-decessi-coronavirus-maggio-2020.html
  7. https://www.ecdc.europa.eu/en/publications-data/using-face-masks-community-reducing-covid-19-transmission
  8. https://publikationen.dguv.de/regelwerk/dguv-regeln/1011/benutzung-von-atemschutzgeraeten
  9. https://www.vasodipandora.net/2020/05/29/coronavirus-and-masks/
  10. www.salute.gov.it/portale/covid/SISMG_sintesi_ULTIMO.pdf del 15/6/2020
  11. https://www.vasodipandora.net/2020/05/29/der-weltbildzertruemmerer-wegener-und-das-coronavirus/
  12. https://www.vasodipandora.net/2020/05/29/aerosol-als-der-einzig-relevanter-uebertragungsweg-des-coronavirus-epidemiologische-analyse/
  13. https://link.springer.com/chapter/10.1007/978-3-642-29942-1_16
  14. https://www.vasodipandora.net/2020/07/26/luft-ist-leben/
  15. https://pubmed.ncbi.nlm.nih.gov/12950586/   Rudnick and Milton
  16. https://www.tagesspiegel.de/gesellschaft/erster-ausbruch-des-marburg-virus-was-vor-50-jahren-in-den-behringwerken-geschah/20176074.html
  17. https://www.vasodipandora.net/2020/05/29/modell-zur-erklaerung-der-geringen-infektionsrate-bei-kindern-durch-das-coronavirus-epidemiologische-anatomische-und-physiologische-analyse/
  18. https://eur-lex.europa.eu/legal-content/IT/LSU/?uri=CELEX:32001L0020
  19. https://www.google.com/search?q=Comitato+etico+(CE)+-+EUPATI&oq=Comitato+etico+(CE)+-+EUPATI&aqs=chrome..69i57j33l3.6976j0j4&sourceid=chrome&ie=UTF-8
  20. https://www.vasodipandora.net/2020/07/26/children-and-coronavirus/

Correlated articles

General observations on the Coronavirus

The aerolsol as the only significant mode of transmission of the coronavirus: epidemiological evidence

Model to explain the low incidence of the coronavirus infection in children: epidemiological, anatomical and physiological analysis

.https://www.vasodipandora.net/2020/05/29/modell-zur-erklaerung-der-geringen-infektionsrate-bei-kindern-durch-das-coronavirus-epidemiologische-anatomische-und-physiologische-analyse/

Protective effect of smoking against Coronavirus

Coronavirus and masks

Air is live

Children and Coronavirus


La verità è come un leone. Non avrai bisogno di difenderla. Lasciala libera. Si difenderà da sola, oppure: LA VIA SBAGLIATA: ANALISI DELLE MISURE ANTI CORONAVIRUS E DEI MOTIVI PER IL LORO FALLIMENTO

Riassunto:

Il coronavirus, un virus ben noto da più di mezzo secolo e paragonabile all’influenzavirus, ha allarmato gran parti dei governi. Ritenendo quale via di trasmissione quella tramite contatto e goccioline, sono state intraprese delle misure per affrontare l’emergenza, le quali si dimostrano non solo inefficienti ma addirittura dannose. Così viene spianata la strada alla vaccinazione, superflua e di potenziale pericolosità come tutte le vaccinazioni innovative. Sulla vera via di trasmissione del virus, che avviene esclusivamente attraverso aerosol, non si interviene, aggravando giorno per giorno la situazione globale.

L’inizio della virologia risale al 1780 ante Cristo (Codex Eschnunna) (1), dove fu descritto un caso di rabbia. Cornelius Aulus Celsus (2 )nel primo secolo ante Cristo assegnava all’agente di tale malattia la definizione virus, nel 1882 Adolf Mayer (3) e nel 1898 Martinus Willem Beijjerinck (4) indicavano l’esistenza di un agente infettivo non filtrabile e non dimostrabile con le metodiche alla loro disposizione. L’avvento del microscopio elettronico nel 1931 ha confermato la loro teoria e la virologia è diventata una scienza.

Questa scienza si è vista confrontata con il coronavirus, un virus respiratorio già noto da più di mezzo secolo e già allora studiato nei particolari (5) che ha creato una pandemia da inserire in una lunga lista di epidemie e pandemie dei tempi recenti. L’approccio a tale evento è stato però subito discusso nel mondo virologico in maniera molto contrastante, un fatto inusuale per una scienza affermata (1+1=2, né 3 né 4).

I vari governi europei, allarmati dal decorso della epidemia, hanno più o meno adottato le stesse misure di prevenzione della trasmissione quali: dispositivi protettivi (mascherine e guanti), limitazioni allo spostamento, distanziamento anche all’aperto, individuazione ed isolamento di portatori sani.

ANALISI DEI FATTORI PREDISPONENTI DEMOGRAFICI E GEOGRAFICI

Prima di analizzare l’efficacia di tale misure protettive sulla epidemia, bisogna considerare altri fattori predisponenti e fondamentali che incidono sul decorso delle curve (l’Italia viene considerata rappresentativa per i seguenti aspetti per gran parte dei paesi europei).

  1.  Aspetto demografico italiano

Dal 2010 il numero dei ultranovantenni è passato da circa 400 mila a circa 700 mila nel 2017. Nel 2018 le persone registrate con l’età sopra gli 85 anni sono 2.2 milioni (valore più alto dell’Europa). Questo comporta un continuo aumento del numero delle persone anziane in case di riposo. Attualmente sono più di 300 mila anziani ospiti di strutture in Italia. Questo numero corrisponde alla città di Venezia con i suoi 260 mila abitanti, i suoi circa 60 mila turisti giornalieri ed i suoi gondolieri inclusi.

Italia di giorno
Italia di notte
Italia e l’epidemia da Coronavirus


Il 91% dell’eccesso di mortalità avviene nelle zone del nord con un aumento del 52%, nelle altre zone si passa da un aumento medio della mortalità del 1.1% fino ad una riduzione addirittura del 5% della mortalità in Sicilia. Ad essere colpite sono le zone del nord, quelle più industrializzate con i loro fattori specifici ambientali, climatici e lavorativi.

ANALISI DELLE MISURE DI PREVENZIONI

Un ruolo significante delle mascherine in relazione di trasmissione di malattie virali respiratori (7) non è mai stata dimostrato scientificamente. Inoltre il consiglio/obbligo di indossarli non tiene conto delle normative vigenti (8) circa il loro utilizzo (essendo dispositivi di lavoro) per quanto riguarda il tempo di utilizzo e l’uso in persone con patologie cardio-respiratorie, per donne incinte e per bambini. La mancata informazione dei rischi derivanti dal loro uso comporta un grave rischio per la salute pubblica con danni anche irreversibili a lungo termine (9). Ma nonostante questo in tutto il mondo viene consigliato l’uso delle mascherine, forse solo per tranquillizzare il popolo.

Anche il distanziamento per ridurre la trasmissione del virus nella popolazione non trova alcun riscontro nella letteratura medica per quanto riguarda una eventuale riduzione della mortalità relativa a malattia respiratori influenzali e simili. Nonostante questo, tale misura resta tutt’oggi esteso su pressoché qualsiasi ambiente di vita sia all’aperto (anche sulla spiaggia, al mare, allo stadio, feste al pubblico padronali, religiose ecc.), che in ambienti chiusi.

ANALISI DELL’EFFICACIA DELLE MISURE

Non sono state riscontrate variazioni significative sul decorso della mortalità dopo l’applicazione di tale misure. Le curve di mortalità da Influenzavirus del 2016/2017 e quella da Coronavirus presentano un andamento statisticamente sovrapponibile.

www.salute.gov.it/portale/covid/SISMG_sintesi_ULTIMO.pdf  del 15/6/2020 (10)

Esse rappresentando due curve di Gauss con identici parametri di pendenza eccetto l’altezza delle curve. Detraendo dal picco della curva la ridotta mortalità dei mesi precedenti alla epidemia da Coronavirus (novembre e dicembre 2019 e gennaio, febbraio 2020), le curve sono sovrapponibili.

ANALISI DEI MOTIVI DI INSUCCESSO DELLE MISURE INTRAPRESE

Il motivo per l’insuccesso delle misure intraprese, responsabili del continuo aumento di morti, dipende dall’insistenza sulla via sbagliata di trasmissione (vedi titolo), considerata anticamente tramite goccioline o per contatto. La via di trasmissione del coronavirus invece consiste esclusivamente in quella attraverso l’aerosol, come già indicata il 21/4/2020 alla comunità scientifica (Considerazioni generali sul Coronavirus (11), L’aerosol quale unica via rilevante di trasmissione da coronavirus (12)) e poi anche a vari enti statali e non, finalmente accettata dalla Organizzazione Mondiale della Salute (OMS).

Il virus si comporta nell’aria come le particelle sospese del fumo, che hanno dimensioni paragonabili (13).

Queste evidenze vengono ulteriormente rafforzato da osservazioni in Germania, dove molte persone in ambienti chiusi sono state infette (comitiva di coro (8), più di 1500 lavoratori di un matatoio (9)). L’elevata carica virale, presente sotto forma di aerosol, era dovuta in questi casi alla presenza di persone asintomatiche in fase infettiva e alla coesistenza di altri fattori, fra quali la cospicua emissione del virus per aumentata attività respiratoria (coro), la maggiore persistenza del virus nell’ambiente causato dalla temperatura basse di lavoro (mattatoio) e dalla aerazione insufficiente per ridurre la dispersione sonora (coro) ed energetica (mattatoio).

CONSIDERAZIONI SULLA RISPOSTA NATURALE AL CORONAVIRUS

La trasmissione pericolosa per la salute avviene in ambienti chiusi (case di riposo, posti di lavoro, uffici, ospedali, metropolitane, sale di congresso ecc.), dove la elevata carica virale a causa della insufficiente aerazione (14) porta spesso ad una evoluzione grave, specie in persone con patologia preesistenti. Come largamente dimostrato, la qualità dell’aria in tali ambienti è in stretto rapporto con il rischio di contrarre malattie infettive respiratorie (15) e nel caso specifico da coronavirus.

In ambienti aperti, ma anche in ambienti chiusi, ben aerati, tale trasmissione avviene solo con una carica virale molto bassa, paragonabile ad un vaccino attivo, che induce una risposta immunologica senza evidenti segni di malattia.

Antropologicamente nelle communita chiuse lo straniero fu escluso, considerandolo un pericolo: distanziamento, mentre entro la comunità furono applicati le misure di anti-distanziamento per garantire un passaggio di agenti infettive trasmesso da aerosol (virus) anche all’aperto. Nei paesi del Nord Europa bastava per tale via di trasmissione avvicinarsi a meno di un metro, cioè quella distanza di stringersi la mano. Nei paesi più caldi l’aerosol è più instabile nell’aria, per cui c’è bisogno di un avvicinamento più intimo (bacetto sulla guancia), Nelle zone polari, rendendo impossibile una trasmissione a distanza, essa era assicurata esclusivamente strofinandosi i nasi.

Se l’umanità avesse applicato le leggi disposte attualmente da gran parte dei governi, essa farebbe già da tempo parte delle specie estinte.

Per questo il fattore di replicazione, che indica quante persone vengono infettati da una persona infettata, deve essere alto nella popolazione sana (ovviamente persone anziane o con patologie concomitanti vengono cautelate, come avvenuto da sempre), garantendo così la memoria immunologica indispensabile per la sopravvivenza del homo sapiens.

L’individuazione di positivi tramite l applicazioni tipo app immune o tramite esami di massa (con costi non indifferenti per la comunità) ed il loro isolamento, interviene gravemente sul decorso naturale della difesa dell’uomo verso le malattie infettive. Così si crea artificialmente la necessità di un vaccino sempre con ulteriori costi non indifferenti per la comunità.

‘E da temere, che l’aumento della mortalità fine estate, che si ripete ogni anno come il picco invernale nel corso delle epidemie influenziali, verrà attribuita al Coronavirus (come già annunciato da mesi), che confermerà l’immediata necessità nazionale del vaccino.

CONSIDERAZIONI SULLA VACCINAZIONE

Attualmente i trials di vaccini nel mondo secondo l’OMS sono più di 140 con sperimentazioni multipli su persone, tutte in fase accelerata per l’emergenza, con i pericoli inerenti per i volontari ma anche per i addetti alla sperimentazione (vedi l’esperienza terrificante nel 1967 per il virus Marburg (16)). Inoltre nella fase 2 sono previsti come volontari bambini, in netto contrasto con le direttive UE (17). Queste affermano che “questo obiettivo può essere raggiunto soltanto attraverso una sperimentazione approfondita dei farmaci che possono avere una notevole rilevanza clinica per i bambini”. Questa rilevanza clinica per i bambini non esiste, perché non vengono colpiti dal coronavirus (18), come dimostrata da gran parte della letteratura.

Considerando i rischi inerenti alla sperimentazione, sarebbe stato forse più prudente, limitarli a pochi centri nel mondo, autorizzati da comitati etici, che sono, come postulato dall’Accademia Europea dei Pazienti (19): indipendenti da “sponsor, finanziatori, sperimentatori e da influenze indebite (ad es. politiche, istituzionali, professionali o commerciali.

Il vaccino, alla fine ottenuto da queste sperimentazioni multipli, che non rispettando i tempi normalmente considerati necessari per garantire un vaccino sicuro, mette a serio rischio le persone da sottoporre alla vaccinazione, con danni attualmente non quantificabili ma potenzialmente gravissimi. Chiunque medico deve ricordarsi del giuramento di Ippocrate e deve opporsi almeno all’obbligo della vaccinazione dei bambini, per i quali non sussiste nessun beneficio da tale trattamento ma solo elevati rischi.

CONCLUSIONI

Non intervenendo sulla unica via di trasmissione del virus (aerosol) si continua di esporre le popolazioni ad un grave rischio per la loro salute. Le precauzioni da intraprendere sono né mascherine (dannosi) né distanziamento (controproducente), ma consistono in una adeguata aerazione dei edifici.

Se non verranno intraprese le dovute misure preventive in tale senso, una ulteriore pandemia causato da un altro virus allarmerà di nuovo il mondo politico con tutte le conseguenze già vissute quest’anno.

La storia della medicina è stata impregnata da grandi personalità, che non hanno mai temuto il contatto con i malati, quali Madre Teresa di Calcutta, Pasteur, Koch, Virchow, e da grandi protagonisti della storia della virologia. Non facciamo distruggere la loro memoria ed il loro impegno, costruendo la medicina su falsi presupposti, che alla fine colpiranno i più deboli, i nostri figli (20).

BIBLIOGRAFIA

  1. https://www.google.com/search?q=codex+eschunna&oq=codex+eschunna&aqs=chrome..69i57j0l2.8426j0j4&sourceid=chrome&ie=UTF-8
  2. https://www.cambridge.org/core/journals/classical-review/article/celsus-de-medicina-aulus-cornelius-celsus-ueber-die-artzneiwissenschaft-ubersetzt-und-erklart-von-eduard-scheller-zweite-auflage-von-walther-frieboes-braunschweig-vieweg-und-sohn-1906-8vo-pp-xlii-862-tafeln-iv-m-18/083432E6C5C31FB9539507FA69583E42
  3. https://www.buecher.de/shop/fachbuecher/adolf-mayer-agronom/broschiertes-buch/products_products/detail/prod_id/31684669/
  4. https://www.britannica.com/biography/Martinus-W-Beijerinck
  5. https://www.vasodipandora.net/2020/05/30/virus-da-poco-conosciuto-e-ben-conosciuto-decenni/
  6. https://www.udinetoday.it/attualita/indagine-inps-decessi-coronavirus-maggio-2020.html
  7. https://www.ecdc.europa.eu/en/publications-data/using-face-masks-community-reducing-covid-19-transmission
  8. https://publikationen.dguv.de/regelwerk/dguv-regeln/1011/benutzung-von-atemschutzgeraeten
  9. https://www.vasodipandora.net/2020/05/24/coronavirus-e-maschere/
  10. www.salute.gov.it/portale/covid/SISMG_sintesi_ULTIMO.pdf del 15/6/2020
  11. https://www.vasodipandora.net/2020/05/25/considerazioni-generali-sul-coronavirus/
  12. https://www.vasodipandora.net/2020/05/24/laerosol-quale-unica-via-rilevante-di-trasmissione-del-coronavirus-evidenze-epidemiologiche/
  13. https://link.springer.com/chapter/10.1007/978-3-642-29942-1_16
  14. https://www.vasodipandora.net/2020/07/24/laria-e-vita/
  15. https://pubmed.ncbi.nlm.nih.gov/12950586/   Rudnick and Milton
  16. https://www.tagesspiegel.de/gesellschaft/erster-ausbruch-des-marburg-virus-was-vor-50-jahren-in-den-behringwerken-geschah/20176074.html
  17. https://eur-lex.europa.eu/legal-content/IT/LSU/?uri=CELEX:32001L0020
  18. https://www.vasodipandora.net/2020/05/24/modello-per-spiegare-la-bassa-incidenza-della-infezione-da-coronavirus-in-bambini-analisi-epidemiologica-anatomica-e-fisiologica/
  19. https://www.google.com/search?q=Comitato+etico+(CE)+-+EUPATI&oq=Comitato+etico+(CE)+-+EUPATI&aqs=chrome..69i57j33l3.6976j0j4&sourceid=chrome&ie=UTF-8
  20. https://www.vasodipandora.net/2020/07/24/bambini-e-coronavirus/

ARTICOLI CORRELATI

Considerazioni generali sul Coronavirus

L’aerosol quale unica via rilevante di trasmissione  del Coronavirus: evidenze epidemiologiche

Modello per spiegare la bassa incidenza della infezione da Coronavirus in bambini, analisi epidemiologica, anatomica e fisiologica

Effetto protettivo del fumo contro il Coronavirus

Coronavirus e mascherine

L’aria è vita

Bambini e Coronavirus

Read the article in english :

Lesen Sie den Artikel auf Deutsch